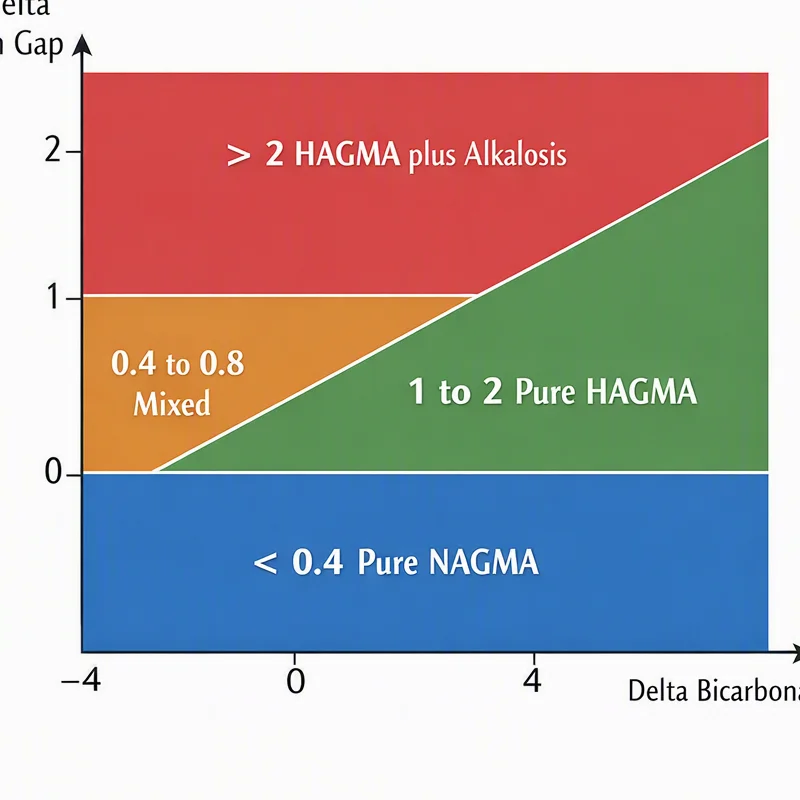
What Is Starvation Ketoacidosis?
starvation ketoacidosis is one type of metabolic acidosis that occurs when the body does not receive enough carbohydrate or overall fuel and starts depending largely on fat for fuel. This shift leads to ketosis, a state in which the liver produces ketone bodies to deliver energy. When this process becomes more intense, acid production rises enough to alter acid-base balance and change laboratory values.
The trigger is usually fasting, prolonged poor intake, or malnutrition. In these settings, the body experiences an energy deficit and a gradual drop in circulating glucose availability. As glucose availability declines, the body increases fat metabolism, which raises ketoacid production. This is different from everyday short-term ketosis because starvation states can produce a clinically meaningful acid-base disturbance.
Starvation ketoacidosis often occurs when nutritional deprivation is severe enough that the liver generates more acidic byproducts than the body can easily buffer. The main ketone-related acids are beta-hydroxybutyrate and acetoacetate. These compounds are part of normal ketone physiology, but in excessive amounts they contribute to metabolic derangement and a recognizable pattern of high anion gap metabolic acidosis.
Understanding this process matters because not all ketosis is the same. In starvation ketoacidosis, the key issue is not simply the presence of ketones, but the combination of glucose depletion, acid generation, and the resulting change in laboratory interpretation. That is why the Anion Gap Calculator can be valuable as a quick tool for clinical interpretation of the lab pattern.
How starvation ketoacidosis Elevates the Anion Gap
The anion gap goes up when acids accumulate in the blood and their charged components are not directly measured in a standard electrolyte test. In starvation ketoacidosis, the major cause is the buildup of unmeasured anions produced from ketone bodies. As beta-hydroxybutyrate and acetoacetate increase, they deplete buffering capacity and leave behind negatively charged acid metabolites that elevate the gap.

This is the classic mechanism of a high-gap acidosis. The body reacts to acid buildup by lowering bicarbonate, which is the primary buffer consumed during acidosis. As bicarbonate falls, the gap often rises because the lost buffer is functionally replaced by acidic anions that are not directly reflected in routine chemistry values.
The process is driven by ketone accumulation during prolonged fasting or nutritional deprivation. When insulin levels are relatively low and glucose intake is insufficient, the body shifts toward ketone production for fuel. This adaptive response becomes harmful when ketone generation outpaces utilization and elimination. The resulting organic acids shift acid-base balance and produce the elevated anion gap seen on labs.
Although both ketone bodies contribute, beta-hydroxybutyrate is often the dominant acid in more significant ketoacid states. Acetoacetate also adds to the measured acid load, but the total burden depends on severity, duration, and physiologic stress. The important point is that the ketones function as organic acids, and their presence explains why starvation ketoacidosis is a true cause of anion gap calculation abnormalities rather than a benign lab curiosity.
Put simply: starvation creates an energy shortage, the body burns fat, fat metabolism yields ketones, and those ketones act as unmeasured acids. That chain of events is why the anion gap increases.
How to Work Out and Understand the Anion Gap
An Anion Gap Calculator can assist in estimate whether the electrolyte pattern suggests a elevated-gap acidosis. The standard calculation is based on sodium, chloride, and bicarbonate:
Anion gap = sodium - (chloride + bicarbonate)
This formula is simple, but interpretation depends on the overall clinical setting. A higher-than-expected result points to too many unmeasured anions, while a typical result makes starvation ketoacidosis less probable or may reflect an initial / weaker stage. Because reference ranges vary by lab, the exact cutoff should be read alongside the laboratory-specific values and the patient’s overall picture.
In starvation ketoacidosis, the gap increases because bicarbonate is consumed to buffer the acids produced by ketogenesis. The low bicarbonate often parallels the severity of acidosis. Meanwhile, chloride may appear relatively normal or may rise in mixed patterns depending on volume status and replacement fluids. Sodium is required for the calculation and may also change with dehydration, poor intake, or concurrent illness.
When working with an Anion Gap Calculator, it can help to think in terms of clinical interpretation rather than a single value. A somewhat elevated gap may still be meaningful if the patient has clear malnutrition, repeated vomiting, poor food intake, or visible ketosis. A markedly high value suggests a more intense metabolic acidosis or another concurrent cause of high anion gap metabolic acidosis.
For interpreting the result effectively, pair the gap with the rest of the laboratory picture:
- Sodium: helps anchor the overall calculation and evaluate hydration or dilutional effects. Chloride: helps clarify whether the acidosis is accompanied by compensatory or mixed changes. Bicarbonate: typically decreases as acid load increases and is a key marker of disease intensity.
This calculation is merely one piece of the puzzle. The aim is not only to spot an out-of-range result, but to connect it to the pattern of ketosis, acid-base disturbance, and the possible cause of the metabolic imbalance.
Characteristic Laboratory Findings in Starvation Ketoacidosis
Starvation ketoacidosis has a recognizable laboratory pattern, although the exact pattern varies depending on the duration of fasting, degree of malnutrition, and any associated illness. The most helpful tests often include serum glucose, electrolytes, arterial blood gas, and serum ketones.
Serum glucose is frequently normal or low rather than markedly elevated. One of the main clues separating starvation ketoacidosis from other forms of ketoacidosis. Because the underlying problem is lack of intake rather than excess glucose, the glucose level may reflect exhaustion rather than hyperglycemia.
Electrolytes often show the biochemical signature of acid-base stress. The bicarbonate level is usually low, supporting the diagnosis of metabolic acidosis. Sodium and chloride may vary depending on fluid losses, vomiting, dehydration, or treatment before testing. Assessing the entire set of serum electrolytes helps determine whether the picture is pure or mixed.
Serum ketones are typically positive, and if quantitative testing is available, elevated beta-hydroxybutyrate supports the diagnosis more strongly than a basic urine ketone screen alone. This is because urine ketone testing may underrepresent the burden of beta-hydroxybutyrate. In starvation states, beta-hydroxybutyrate can be disproportionately elevated and is a major driver of the acid load.
An arterial blood gas may show acidemia with a low bicarbonate and compensatory respiratory changes. A patient may develop compensatory hyperventilation as the body tries to lower carbon dioxide and offset the acid load. This respiratory https://anion-gap-widget225.almoheet-travel.com/anion-gap-calculator-with-serum-bicarbonate-interpreting-the-results response helps maintain pH, but it does not correct the underlying problem.
Typical findings may include:
- Low or normal serum glucose Low bicarbonate Positive serum ketones Elevated beta-hydroxybutyrate and acetoacetate Abnormal electrolytes Acid-base changes on arterial blood gas
These findings support the diagnosis, but they also help estimate severity. The more pronounced the acidosis and ketone burden, the more likely the anion gap is to be clearly elevated.
How It Differs With Diabetic Ketoacidosis and Other Causes
Starvation ketoacidosis can resemble other causes of high anion gap metabolic acidosis, so separating it from related conditions is important. The closest mimic is diabetic ketoacidosis, but there are several distinctions.
In diabetic ketoacidosis, the core issue is insulin deficiency, which triggers severe ketone production and usually produces significantly higher glucose levels. Starvation ketoacidosis, by contrast, is driven by glucose depletion and inadequate intake. The patient may have normal or low glucose rather than marked hyperglycemia. That distinction changes both the diagnostic thinking and treatment priorities.
Alcoholic ketoacidosis is another important differential. It often occurs after poor intake combined with heavy alcohol use and may resemble starvation physiology. Like starvation ketoacidosis, it can produce ketone-related acids and an elevated anion gap. The broader context, however, differs, and alcohol use can add extra metabolic complexity.
Lactic acidosis is another major cause of anion gap elevation. Instead of ketone bodies, lactate is the main unmeasured anion. Lactic acidosis may occur with tissue hypoperfusion, sepsis, or other forms of metabolic stress. If lactate is elevated, it can explain part or all of the gap, even if ketosis is present at the same time.
Renal failure can also raise the gap because failing kidneys cannot clear acids effectively. In that setting, retained acids and other retained solutes contribute to the anion gap. Renal impairment can coexist with starvation or dehydration, which makes interpretation more difficult and reinforces the need for careful diagnostic evaluation.
The key differences often come down to the pattern of labs and the clinical story:
- Diabetic ketoacidosis: usually marked hyperglycemia and insulin deficiency Starvation ketoacidosis: fasting, malnutrition, low or normal glucose, ketone-driven acidosis Alcoholic ketoacidosis: alcohol use plus poor intake, overlapping metabolic features Lactic acidosis: elevated lactate from hypoperfusion or stress Renal failure: impaired acid clearance and retained metabolic acids
Because these conditions can overlap, the best approach is to use the anion gap as a beginning point, not the final diagnosis. The gap identifies the presence of excess unmeasured anions, but only the rest of the clinical picture can determine the cause.
When a High Anion Gap Needs Immediate Evaluation
A raised anion gap always requires attention, but the level of concern depends on the severity, accompanying symptoms, and the general acid-base disorder. Starvation ketoacidosis may be mild in some cases, but it can still become severe if the patient is dehydrated, not able to eat, or has another illness adding to the metabolic disturbance.
Prompt evaluation is necessary when symptoms suggest worsening acidosis or systemic illness. These may include disorientation, significant weakness, persistent vomiting, increased respiratory rate, dehydration, or inability to maintain intake. A patient with clear acidemia on an arterial blood gas and an elevated gap needs prompt clinical assessment rather than mere observation.
The concern is not only the ketones themselves, but the overall acid-base balance. If bicarbonate continues to fall, the acidosis can intensify. If the patient has concurrent infection, vomiting, renal impairment, or significant volume depletion, the metabolic picture can worsen quickly.
Useful considerations during assessment include:
- How long the patient has had reduced intake or fasting Whether there is malnutrition or ongoing lack of adequate nutrition Evidence of ketosis or marked ketone burden Whether serum glucose is below normal, normal, or elevated Whether another cause of high anion gap metabolic acidosis may also be present
If the patient is symptomatic or the laboratory values show a major metabolic derangement, the issue should be treated as not just a simple electrolyte abnormality. The elevation in the anion gap is a marker of underlying acid production, and the source for that acid load must be identified.
Common Questions About fasting ketoacidosis and Anion Gap
Can starvation ketoacidosis always cause a high anion gap?
Not necessarily, but it often does. Starvation ketoacidosis typically increases the anion gap because ketone-related acids create unmeasured anions. In mild or mild cases, the gap may be only mildly increased or even appear close to normal if the acid load is limited or if other electrolyte changes are present. The overall clinical context and anion gap interpretation are important as much as the number itself.
How high is the anion gap in fasting ketoacidosis?
The level of elevation differs with the severity of ketosis, duration of fasting, and presence of other illnesses. Some cases show a slight to moderate rise, while more severe starvation ketoacidosis can produce clear high anion gap metabolic acidosis. The exact level is not as important than whether the result matches the rest of the picture, including bicarbonate, serum glucose, and ketone testing.
What lab tests are useful to confirm ketoacidosis from starvation?
The most useful tests include serum glucose, electrolytes, arterial blood gas, and serum ketones. Quantitative beta-hydroxybutyrate is especially helpful because it reflects the main ketone burden more accurately than some urine tests. These results, combined with the history of poor intake or malnutrition, support the diagnosis.
In what way is starvation ketoacidosis different from diabetes-related ketoacidosis?
Diabetic ketoacidosis is driven by insulin deficiency and usually presents with much higher glucose levels. Ketoacidosis from starvation is caused by glucose depletion from inadequate intake and often has typical or low serum glucose. Both can produce ketosis and elevated anion gap acidosis, but the trigger, lab pattern, and treatment approach differ.
Can the anion gap normalize to expected levels after care?
Yes. As the underlying problem is treated, ketone production drops, unmeasured anions lessen, and the anion gap can return toward normal. Care usually focuses on the energy deficit, fluid replacement, and electrolyte imbalances, which helps restore acid-base balance. Repeat laboratory values are often used to confirm improvement in metabolic acidosis and overall metabolism.
Starvation ketoacidosis is a real acid-base problem, not just a simple ketotic state. The key pattern is the rise in the anion gap from ketone-related organic acids, especially beta-hydroxybutyrate and acetoacetate, during periods of fasting or malnutrition. An Anion Gap Calculator helps you identify that pattern efficiently, but the most precise interpretation always comes from pairing the calculation with the clinical story, laboratory values, and thorough medical assessment.