An anion gap calculator is a helpful diagnostic tool adjusted anion gap low albumin designed to assist interpret a blood chemistry panel or electrolyte panel. It brings together serum sodium, chloride, and bicarbonate to produce a calculated value that aids clinical interpretation of acid-base balance. While the number itself is straightforward, the meaning behind it depends on the complete lab result, including albumin, the entire electrolytes, and the patient’s assessment.
This guide explains how the anion gap functions, how the anion gap formula relies on sodium and related measurements, and why the result can point toward a specific metabolic disturbance such as metabolic acidosis or high anion gap metabolic acidosis. It also covers albumin correction, corrected anion gap use, reference range interpretation, and important diagnostic limitations.
What this Anion Gap Measures
The anion gap calculates the gap between observed positive and negative ions in the blood. In plain language, it helps identify whether there are extra unmeasured ions in the body that may affect the body’s acid-base balance. As the body keeps electrolytes in a narrow range, even small shifts in serum sodium, chloride, and bicarbonate can provide useful indications.
Most clinicians rely on the anion gap as part of a broader serum chemistry review. It is not a standalone finding. Instead, it is one piece of evidence that can refine the interpretation of a metabolic acidosis workup, especially when a patient has symptoms or other abnormal lab findings.
The idea behind the anion gap is that sodium is usually the main measured positive ion, while chloride and bicarbonate are two of the main measured negative ions. The gap reflects what is not directly measured. That is why the result can be helpful when looking for hidden causes of a metabolic disturbance.
Anion Gap Calculation Formula
A standard anion gap formula is simple:
Anion gap = sodium - (chloride + bicarbonate)
A few calculators include potassium, but it is often excluded in modern references for ease. The essential inputs are the sodium concentration, chloride level, and bicarbonate level. When these values are entered into an anion gap calculator, the tool gives a rapid measurement that can be compared with the usual reference range.
For instance, if the sodium is 140, the chloride is 102, and the bicarbonate is 24, the calculation is:
140 - (102 + 24) = 14
That calculated value may fall within many commonly used normal limits, depending on the lab. Because ranges vary, the result should always be interpreted in relation to the specific laboratory’s reported range and the overall clinical interpretation.
In use, the anion gap calculator is valuable because it streamlines the interpretation of a routine blood chemistry panel. The calculator does not replace judgment; it structures the data so patterns become easier to recognize.
How Blood Sodium Affects the Result
Serum sodium is fundamental to the formula because it supports the formula. Since sodium is the largest measured cation in the blood, any change in its concentration can alter the anion gap result. That does not mean sodium directly causes the acid-base problem, but it can influence the final number and how the electrolyte balance is evaluated.
If sodium is low or high, the relationship between sodium, chloride, and bicarbonate changes. The resulting lab result may still be informative, but the context matters. For example, a low sodium value can make the calculated gap less clear to interpret if the rest of the electrolytes are altered at the same time.
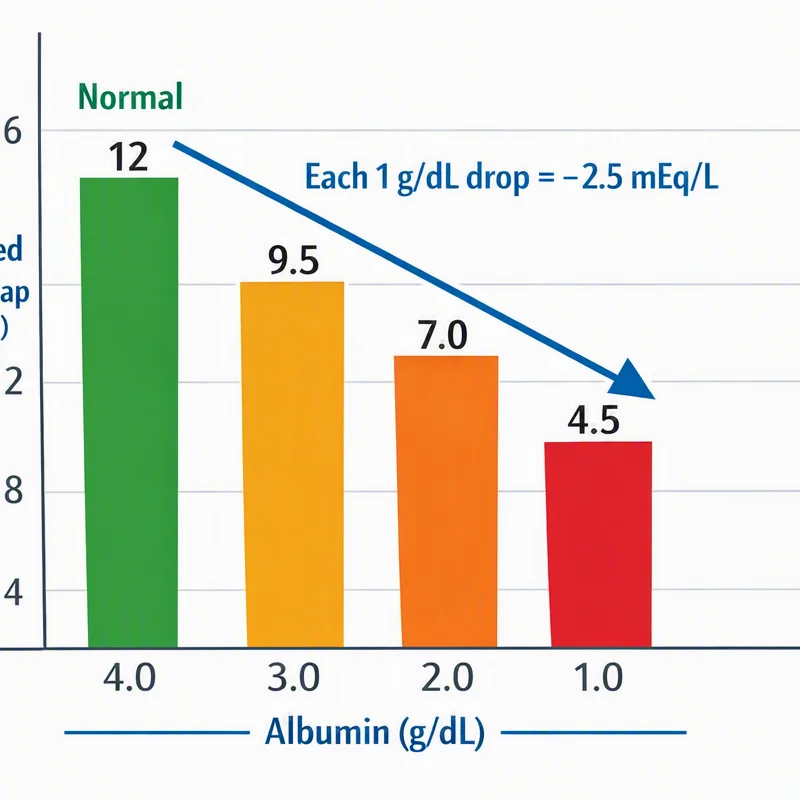
Albumin also matters here. Because albumin is a negatively charged protein, lower albumin can make the anion gap appear lower than it truly is. This is why albumin correction is sometimes used to estimate a corrected anion gap. In a patient with hypoalbuminemia, the unadjusted number may downplay the degree of underlying acid-base abnormality.
The corrected result is not a separate diagnosis. Rather, it is a correction factor applied to improve interpretation. This is especially important when the goal is to investigate a hidden cause of metabolic acidosis or to detect a subtle change in serum chemistry.
Normal, High, and Decreased Anion Gap Results
The expected range for the anion gap depends on the testing method and whether potassium is included. That said, the result is usually categorized as anion gap within normal limits, increased anion gap, or reduced anion gap.
A normal anion gap often suggests that the measured electrolytes are well balanced in a typical way, though it does not automatically mean there is no problem. A increased anion gap metabolic acidosis usually points to the presence of extra acids or unmeasured charged particles in the blood. A decreased anion gap is less common and may reflect low albumin, lab variation, or other issues that affect the measurement.
It is important to remember that “normal” is lab-specific. A result that seems borderline in one setting may be acceptable in another. This is why a full medical interpretation should consider the specific blood chemistry panel, the patient’s symptoms, and the broader acid-base balance.
In practical terms:
- Normal gap: may be seen when the electrolyte pattern does not suggest excess unmeasured acids. Elevated anion gap metabolic acidosis: suggests extra acid accumulation or another process increasing the gap. Decreased anion gap: may indicate hypoalbuminemia, lab variation, or a less common abnormality.
Typical Causes of Altered Anion Gap Values
A number of conditions can affect the anion gap and suggest a specific cause of metabolic acidosis. Common examples include lactic acidosis, ketoacidosis, renal failure, and hypoalbuminemia.
Lactic acidosis occurs when lactate builds up faster than the body can clear it. This can occur with low oxygen delivery, severe illness, or other metabolic stress. Since lactate is an unmeasured anion, the gap may rise.
Ketoacidosis can develop when ketones accumulate, including in uncontrolled diabetes or prolonged fasting. These ketones increase the burden of unmeasured acids, often leading to high anion gap metabolic acidosis.
Renal failure can reduce the body’s ability to eliminate acids. As acid retention increases, the anion gap may become elevated. This finding can be particularly useful when paired with the rest of the electrolytes and kidney-related markers on the blood chemistry panel.
Hypoalbuminemia, on the other hand, may lower the measured gap. Because albumin contributes to the negative charge balance, low albumin can make the result appear deceptively normal or reduced. This is where albumin correction and the corrected anion gap become useful in clinical interpretation.
Other causes can exist too, but these four are among the most often evaluated when reviewing an elevated or reduced anion gap.
Stepwise: Reading Calculator Output
Interpreting an anion gap calculator result is not just entering numbers and seeing a result. A careful process enhances assessment and helps avoid mistakes.
Step 1: Review the electrolyte values. Inspect the serum sodium, chloride, and bicarbonate values from the electrolyte panel or blood chemistry panel. Verify the units and sample are correct.
Step 2: Calculate the anion gap. Use the anion gap formula to obtain the calculated value. Compare it with the lab’s reference range rather than relying on a universal cutoff.
Step 3: Consider albumin. If albumin is low, apply albumin correction to estimate the corrected anion gap. This may show a hidden elevation that would otherwise be missed.
Step 4: Match the pattern to the clinical picture. Identify signs of acid-base disorder, dehydration, kidney dysfunction, or other causes of metabolic disturbance. The result should match the patient’s symptoms and other lab findings.
Step 5: Form a clinical interpretation. A single number is not enough. Synthesize the anion gap with the rest of the serum chemistry, the history, and the physical findings to reach a reasonable conclusion.
A useful anion gap result is one that fits the full story, not one that stands alone.
Constraints of Anion Gap Calculation
Although the anion gap is useful, it has clear limits in diagnosis. The calculation depends on measurement techniques, lab handling, and the situation in which the result is used.
One limitation is albumin adjustment. If albumin is not considered, the result may mislead the interpreter. This is especially relevant in patients with hypoalbuminemia, where the measured gap can be falsely low or normal.
Another limitation is laboratory variation. Different analyzers and reporting methods can produce slightly different reference intervals. A number that seems abnormal in one lab may land in a different lab’s expected interval.
The calculation also does not directly identify the cause of the problem. It simply points to the possible presence of unmeasured charges or a shifted electrolyte pattern. Additional testing and context are needed to confirm the cause, whether that is lactate-related acidosis, ketotic acidosis, renal insufficiency, or something else.
Finally, the anion gap should not be used as a substitute for direct clinical care. It is best viewed as one part of a broader diagnostic approach to pH balance and clinical assessment.
When to Seek Medical Review
Abnormal anion gap findings should be reviewed by a medical professional, especially when they occur with concerning complaints. Signs such as severe weakness, rapid breathing, confusion, vomiting, chest discomfort, or worsening illness may signal a serious acidotic state or another urgent condition.
An elevated or reduced result does not always mean emergency care is needed, but it does mean the test should be understood in context. If a blood chemistry panel shows a concerning pattern, prompt timely assessment anion gap clinical significance may be appropriate to assess the underlying cause.
Individuals with diabetes, kidney disease, infection, dehydration, or known electrolyte abnormalities may need closer assessment if the anion gap is unexpectedly high or low. The same applies if the result changes significantly from prior testing or doesn’t fit the patient’s clinical status.
In case of uncertainty, follow up with a clinician who can assess the result alongside symptoms, exam findings, and other laboratory data.
FAQs About Anion Gap and Serum Sodium
What is an anion gap calculator with serum sodium used for?
An anion gap calculator with serum sodium is used to derive the anion gap from common electrolytes on a blood chemistry panel. It helps with clinical evaluation of acid-base problems, especially when evaluating metabolic acidosis or checking for a hidden metabolic disturbance.
How do you calculate the anion gap from sodium, chloride, and bicarbonate?
Use the anion gap equation: sodium - (chloride + bicarbonate). The sodium level, chloride concentration, and bicarbonate value are entered into the calculator to produce the final value.
Why does serum sodium matter in an anion gap calculation?
Serum sodium matters because it is the main measured cation in the formula. Changes in sodium can affect the final number and the way the acid-base status is interpreted. Sodium also helps anchor the relationship between the measured electrolytes and the overall charge balance.
What does a high anion gap mean?
A high anion gap often suggests extra acids or unmeasured ions in the blood. Common causes include lactic acidosis, ketoacidosis, and renal failure. It can be a clue to high anion gap metabolic acidosis, but the full clinical picture is needed for interpretation.
Can a regular anion gap still suggest a health issue?
Certainly. A anion gap within the normal range doesn't rule out disease or an acid base problem. Some cases may not alter the gap much, and laboratory result review must take into account symptoms, other labs, and the patient’s overall condition. Clinical interpretation should always go beyond the number alone.