What Is the Anion Gap and How Is It Determined?
The anion gap is a calculated value that helps doctors evaluate acid-base balance and detect an underlying metabolic acidosis. It represents the difference between the major measured cations and anions in the blood. In practical terms, it is calculated from the routine electrolyte panel using sodium, chloride, and bicarbonate.
The classic anion gap formula is:
anion gap = sodium - (chloride + bicarbonate)
Because this is a calculated value, it is affected by the accuracy of the underlying lab numbers. A higher-than-expected result suggests that unmeasured anions are present in the bloodstream. These may include organic acids, toxic metabolites, or other compounds that create an electrolyte disturbance and shift the body into an acidotic state.
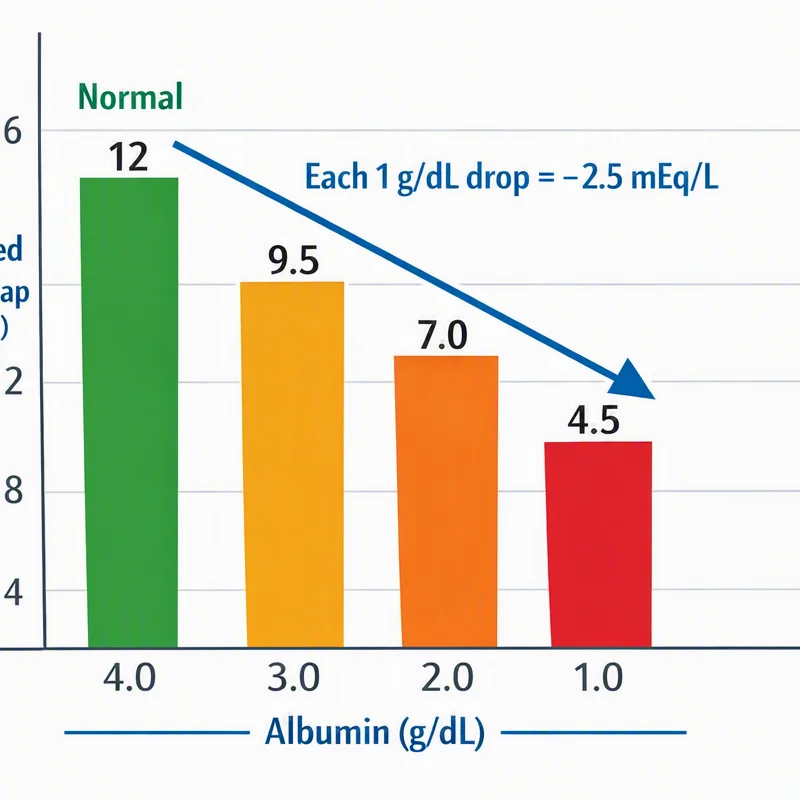
Most clinicians also consider the role of albumin, the main unmeasured anion in blood. Low albumin can lower the apparent anion gap, so the raw number may miss the severity of an anion gap elevation. That is why interpretation always depends on the clinical setting, not the number alone.
The key idea is simple: the anion gap is not a diagnosis. It is a diagnostic clue that can point toward a process such as lactic acidosis, ketoacidosis, renal dysfunction, or toxin-related acidosis.
How an Anion Gap Calculator Helps Interpret Results
An Anion Gap Calculator simplifies the process of working with the formula consistently and efficiently. Rather than estimating the calculation by hand, a clinician or patient can enter the relevant laboratory values and get an immediate result. This can be useful when trying to decide whether a reported lab pattern fits a normal reference interval or suggests an abnormal acid-base process.
Beyond simple calculation, the best use of an Anion Gap Calculator is assessment. A number by itself rarely answers the full clinical question. The result should be viewed in context with symptoms, vital signs, medications, exposure history, and the rest of the chemistry panel.
Many calculators also include albumin correction. This matters because a low albumin level can hide a true gap. Correcting for albumin improves laboratory interpretation and helps avoid missing an important metabolic derangement. If albumin is low, a patient may have significant high anion gap metabolic acidosis even when the uncorrected value appears only slightly elevated.
Using a calculator can also help separate a true metabolic problem from a reporting issue. For example, an electrolyte panel may show a borderline gap, but the presence of low bicarbonate, elevated lactate, or an abnormal blood gas may reveal a more serious process. The calculator therefore supports a broader pattern-recognition approach instead of replacing clinical judgment.
In toxin evaluation, the calculator can serve as an early screen. If the gap is elevated, clinicians may think about exposures that generate unmeasured anions. If the gap is normal but suspicion remains high, further testing may still be needed.
Can Harmful agents Elevate the Anion Gap?
Absolutely. Certain harmful substances can raise the anion gap by producing acids, blocking metabolism, or triggering accumulation of poisonous metabolites. This is a typical cause of high anion gap metabolic acidosis. In these cases, the body retains acidic compounds that are not directly measured on a standard panel, so the gap expands as bicarbonate drops.
A toxic ingestion often causes multiple abnormalities at the same time. The patient may have delta gap value calculator queasiness, retching, dizziness, mental clouding, tachypnea, or greater tiredness. Lab results may show low bicarbonate, rising chloride changes, and an increased anion gap. The resulting pattern depends on the compound involved and how long ago the exposure occurred.
The mechanism is often a form of acid buildup caused by increased acid formation or impaired acid clearance. Some exposures directly produce acids, while others interfere with cellular respiration, creating lactic acidosis or other downstream effects. In all cases, the gap is an indicator of accumulation of unmeasured acidic substances.
Importantly, toxin-related acidosis is not limited to one poison. Several agents can lead to a similar chemistry pattern, which is why exposure history and targeted testing are essential. The anion gap provides an early clue, but not the full diagnosis.
Frequent Toxic Causes of a High Anion Gap
Many toxins are classically linked to a high gap. Key include methanol, ethylene glycol, and salicylates, along with conditions that produce lactic acidosis. These problems can be life-threatening and may present with nonspecific poisoning symptoms.
Methanol is particularly dangerous because it is metabolized into acidic compounds, including formic acid. This leads to acidosis and may also affect vision and the central nervous system. An elevated gap in the setting of exposure history should raise urgent concern.
Ethylene glycol, found in some antifreeze products, is metabolized into glycolic acid and other acids. These toxic metabolites can drive a sharp rise in the anion gap and create kidney injury, neurologic changes, and worsening acidosis.
Salicylates can produce a mixed and evolving picture. Initially, respiratory alkalosis may dominate, but as toxicity progresses, a high gap metabolic acidosis may emerge. Because of this, the lab pattern can change over time and may not be obvious on a single sample.
Lactic acidosis is another major contributor to a high gap. Although not always caused by an external toxin, it can result from impaired tissue oxygen use, shock states, seizures, or severe poison exposure. In toxin evaluation, rising lactate is a major clue that cells are struggling to generate energy normally.
Other poisonings can also contribute, but these are among the most clinically important because they are common, dangerous, and treatable when recognized early. A high gap should prompt consideration of the exposure timeline, associated symptoms, and confirmatory testing.
How Toxic Alcohol compounds Impact pH equilibrium
Poisonous alcohols are among the leading causes of severe anion gap increase. This category includes methanol and ethylene glycol, both of which can first look misleadingly mild before substantial metabolic injury develops. Their danger results from metabolism into very acidic compounds.
These toxins also often produce an increased osmolar gap early in the course. The osmolar gap represents extra osmoles in the blood and can be useful when a toxic ingestion is suspected. With time, as the parent alcohol is metabolized, the osmolar gap may fall while the anion gap increases. That pattern is a major diagnostic clue.
With methanol, the critical toxic metabolite is formic acid. Formic acid contributes to metabolic acidosis and can injure the optic nerve, which is why visual symptoms may be important. With ethylene glycol, glycolic acid and related metabolites promote acidosis and renal injury.
The acid-base effect is not merely a lab curiosity. It reflects a real physiologic emergency in which toxic metabolites accumulate, buffering systems are overwhelmed, and the patient enters a progressively worse acidotic state. That is why treatment decisions often depend on the combination of symptoms, exposure history, blood gas results, and the gap pattern.
In some cases, a patient may have both an elevated osmolar gap and a high anion gap metabolic acidosis. That combination strongly suggests toxic alcohol exposure and requires immediate action. However, neither number alone is sufficient to establish or dismiss the diagnosis.
Other Possible Poisonings and Conditions That Increase the Anion Gap
Not all elevated gap is caused by toxic alcohols. A number of other processes can cause the same picture, including ketoacidosis, renal failure, uremia, and cyanide exposure. These conditions all create accumulation of acids or limit the body’s ability to clear them.
Ketoacidosis occurs when ketone production outpaces the body can use them. This can happen in diabetes, prolonged fasting, or heavy alcohol use. Ketones are organic acids, so they increase the gap and reduce bicarbonate levels.
Renal failure can also raise the gap because damaged kidneys cannot remove acids effectively. When waste products pile up, uremia develops, and the patient can progress into metabolic acidosis. This is one reason kidney function is a component of the standard evaluation for unexplained acidosis.
Cyanide is particularly dangerous because it blocks cellular oxygen utilization. Even if oxygen is present in the blood, cells cannot use it properly, which can rapidly lead to severe lactic acidosis. In this setting, the anion gap may climb as lactate accumulates.
This range of causes matter because a high gap is not exclusive to ingestion. It can also suggest internal illness, tissue hypoperfusion, or organ failure. The challenge is identifying whether the pattern reflects a toxin-related emergency or another severe cause of acid-base disruption.
When a Normal Anion Gap Does Not Rule Out Poisoning
A normal anion gap does not dismiss poisoning. This is especially true in early poisoning, when the toxic substance has not yet been fully metabolized into acidic byproducts. In that stage, the gap may still look normal even while the patient is declining clinically.
Another reason for a misleading result is a mixed acid-base disorder. For example, a patient may have one process increasing the gap and another process lowering it, producing a net value that appears deceptively normal. Nausea and vomiting, hyperventilation, renal disease, or treatment given before labs are drawn can all affect the final number.
That is why clinical suspicion remains crucial. Symptoms, timing, access to toxic substances, mental status, and lab trends matter more than a single snapshot. If the history suggests ingestion, clinicians should not dismiss the possibility simply because the anion gap is not elevated yet.
This point is especially important with toxic alcohols and salicylates, where the laboratory picture can evolve over time. Repeating labs may reveal a developing anion gap elevation even if the first sample is unrevealing.
In short, the gap is a useful clue, but a normal result is not a guarantee of safety.
What Tests Are Used Alongside the Anion Gap?
In cases where toxin induced acidosis is suspected, the anion gap is just one part of the assessment. A blood gas test helps assess pH, bicarbonate status, and whether the body is in an acidic state. It can also show whether a respiratory component is present.
Serum lactate is often checked because increased lactate can help explain a high gap and indicate tissue poor perfusion, convulsions, or toxin contact. Increasing lactate may also suggest significant cellular stress and worsening metabolic derangement.
Ketone levels are important whenever ketoacidosis is possible. Checking ketones can help identify diabetic ketoacidosis, starvation ketosis, or alcohol-related ketosis from other causes of metabolic acidosis.
A tox screen can also help, although common screens do not detect every toxin. Targeted testing for methanol, ethylene glycol, salicylates, or other substances may be needed based on the clinical history and first lab results. This is why targeted testing and supporting clues often work together.
Extra tests can include kidney function studies, osmolality tests, and repeated electrolyte panels. The purpose is to combine the anion gap with the rest of the data so the likely reason can be recognized quickly and therapy can begin.
When It Is Time for Urgent Medical Evaluation
Urgent evaluation is important when toxin contact is suspected and symptoms point to critical illness. Red flags include altered mental status, worsening breathing, persistent vomiting, fainting, seizures, visual changes, or sudden confusion. This situation may suggest a serious acid-base disorder or worsening poisoning.
If you are worried for ingestion, contact the poison center right away and seek emergency treatment if symptoms are severe. Rapid treatment can significantly improve outcomes in prognosis for toxic alcohols, salicylates, cyanide, and other poisons.
Individuals should not wait for symptoms to become serious if the exposure is identified or seriously suspected. Prior to a definitive diagnosis is confirmed, the blend of clinical history, a high anion gap, and supportive lab findings can justify immediate action.
A useful approach is to treat the anion gap as one piece of a wider picture. If the number is high, the patient may need more testing and urgent management. If the number is normal but suspicion remains high, re-evaluation is still necessary because poisoning can progress rapidly.
FAQ
What toxins most commonly increase the anion gap?
The most common toxin-related causes include methanol, ethylene glycol, and salicylates. These can produce high anion gap metabolic acidosis through toxic metabolites, acid accumulation, or both. Severe lactic acidosis from poisoning or tissue injury can also raise the gap.
Can a normal anion gap still happen with poisoning?
Absolutely. A normal anion gap can occur in early poisoning or in a mixed acid-base disorder that masks the abnormality. If clinical suspicion is high, the patient may still need repeat labs and targeted toxicology testing.
How does an Anion Gap Calculator help with toxin evaluation?
An Anion Gap Calculator efficiently calculates the anion gap formula to the patient’s laboratory values. It helps determine whether the result is outside the expected reference interval, assists with identifying anion gap elevation, and can be paired with albumin correction for better laboratory interpretation.
What is the difference between anion gap and osmolar gap?
The anion gap estimates unmeasured anions and is useful for detecting metabolic acidosis. The osmolar gap estimates unmeasured osmoles and is especially helpful in suspected toxic alcohols. In some poisonings, the osmolar gap is high early, while the anion gap rises later as toxic metabolites such as formic acid and glycolic acid accumulate.
When should someone obtain emergency care for potential toxin exposure?
Obtain immediate medical attention at once for potential toxin poisoning with confusion, shortness of breath, fits, intense vomiting, vision changes, or fainting. Call poison control promptly as well. This presentation may signal a severe acid-base disorder that needs immediate evaluation and management.