What the anion gap is and why it matters
The anion gap is a practical way to interpret an electrolyte panel and recognize patterns in acid-base balance. It compares the main measured cations and anions in serum chemistry, aiding clinicians spot hidden acids that do not appear directly on routine lab values. In practical terms, an elevated anion gap can be an useful clue in metabolic acidosis, especially when the cause is not obvious from the initial evaluation.
An anion gap calculator helps translate raw electrolyte data into an actionable result. Rather than looking at numbers in isolation, the calculator aids faster recognition of systemic acidosis, hidden unmeasured anions, and the broader clinical significance of the lab pattern. This is particularly valuable in metabolic acidosis, where the body has a net acid load or a loss of bicarbonate.
In basic terms, the anion gap reflects the difference between measured positive and negative charges in the blood. When the gap is elevated, it often indicates an anion deficit caused by acid accumulation. That makes it a useful diagnostic clue in the workup of an acid-base disorder. It is not a final diagnosis by itself, but it helps focus the differential diagnosis and direct next steps.
How to operate an anion gap calculator
To operate an anion gap calculator, enter the key electrolyte values from the electrolyte panel: sodium, chloride, and bicarbonate. These are the core inputs used in the standard calculation formula. Some tools may also include albumin input so they can provide an adjusted result.
The basic calculation formula is:
Anion gap = sodium − (chloride + bicarbonate)
This formula calculates the gap between measured cations and measured anions. A larger gap generally suggests the presence of additional acids in the blood. Because different laboratories use slightly different methods and reference range limits, the same lab values may produce a different interpretation depending on the calculator and the local lab standard.
For instance, if sodium is 140, chloride is 100, and bicarbonate is 20, the anion gap is 20. That result may be above the expected normal range and therefore raise concern for high anion gap metabolic acidosis. The calculator helps quickly clarify the interpretation, but the clinical picture still matters. Symptoms, kidney function, glucose, lactate, ketones, and medication exposure all affect the next step in the clinical evaluation.
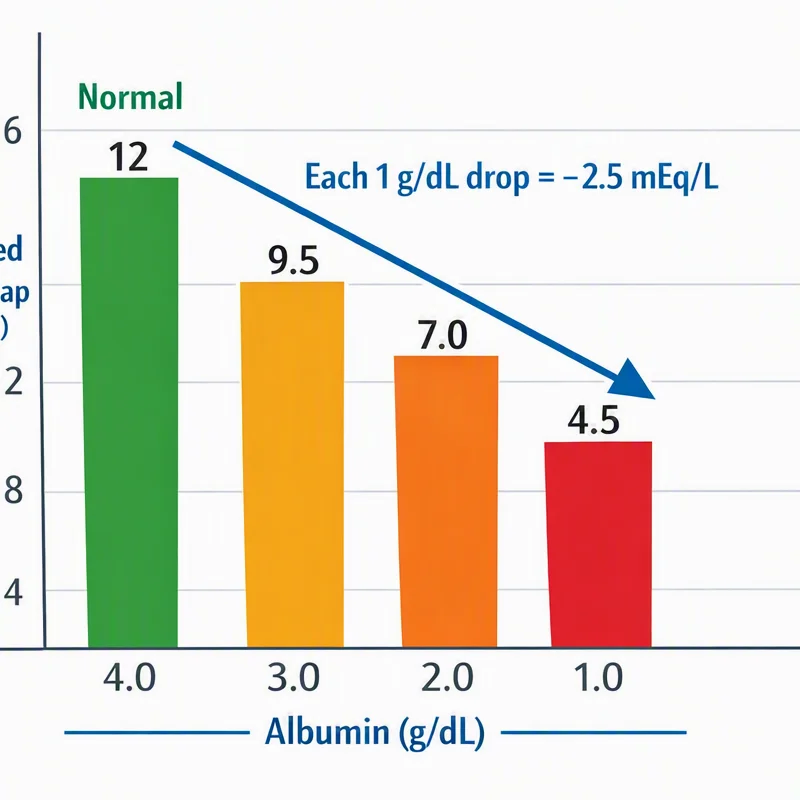
Certain calculators also include albumin, because low albumin can mask an elevated gap. In that case, the displayed adjusted value may be more accurate than the raw result for decision-making.
Normal, high, and low anion gap results
The normal range for the anion gap varies by lab technique, but the overall concept is the same: compare the measured gap to the expected reference interval. A normal result usually suggests either no major accumulation of unmeasured acids or a compensating process that keeps the gap from rising. However, a normal value does not exclude every type of metabolic acidosis.
A high anion gap generally points toward accumulation of acids or unmeasured anions. This is the classic pattern in high anion gap metabolic acidosis. Common causes include lactate accumulation, ketone accumulation, uremic acids, and certain poisonings. The value is best interpreted alongside bicarbonate and pH because it reflects a more significant metabolic derangement, not just a standalone lab abnormality.
A low anion gap is seen less often but can be clinically meaningful. It may occur when albumin is low, when positively charged proteins are present, or when there is a measurement issue. Because albumin contributes significantly to the normal anion gap, hypoalbuminemia can reduce the measured gap and conceal an acid-base problem. In other words, the raw number may fail to show the true burden of unmeasured anions.
When reviewing a result, consider whether the gap aligns with the overall pattern of electrolyte imbalance and the patient’s symptoms. A single number should never be interpreted without context. The key is whether the value supports the suspected acid-base disorder or suggests another process entirely.
Typical causes of high anion gap metabolic acidosis
High anion gap metabolic acidosis usually reflects buildup of acids that lower bicarbonate while creating unmeasured negative charges. The cause often becomes clearer once the clinical context and associated laboratory findings are reviewed.
- Lactic acidosis is often seen in situations of poor tissue perfusion, severe infection, hypoxia, or other conditions that increase lactate production or reduce clearance. Ketoacidosis arises when ketone bodies accumulate and consume bicarbonate. This includes diabetic ketoacidosis, starvation ketosis, and alcohol-related ketosis. Renal failure can reduce acid excretion and allow acid metabolites to accumulate. Related uremia is a classic cause of elevated gap acidosis. Toxins such as toxic alcohols can produce a dangerous rise in organic acids. These exposures require urgent recognition. Salicylates can cause complex acid-base patterns, including an elevated gap with respiratory effects as well.
These causes are important because they reflect different forms of systemic acidosis and may require very different management. For example, lactic acidosis often points to hypoperfusion or severe illness, while ketoacidosis suggests insulin deficiency or carbohydrate deprivation. Renal failure and uremia point toward impaired acid handling, and toxic alcohols and salicylates can demand immediate antidotal or supportive treatment.
That is why the anion gap is so valuable: it does not just label the disturbance, it helps focus the differential diagnosis. The result provides a useful clue that should prompt targeted testing such as lactate, ketones, creatinine, osmolar gap assessment, and toxicology when appropriate.
How the albumin level influences the anion gap
Serum albumin is a important unmeasured anion in the blood, so changes in albumin can significantly affect anion gap interpretation. When albumin is reduced, the measured anion gap may seem normal even when hidden acids are present. This is why low albumin is such an essential consideration in metabolic acidosis workups.
Albumin adjustment refines the raw result to calculate a more accurate albumin-corrected anion gap. This correction helps prevent failure to detect of a true acid load. In practical terms, the corrected anion gap is an adjusted value that accounts for the reduced contribution of albumin to the gap.
A commonly used correction includes extra points to the measured gap for each decrement in albumin below normal. The exact method may change, but the purpose is unchanged: boost the reliability of the result when albumin is abnormal. This becomes especially important when evaluating a patient with metabolic acidosis and unusually normal numbers on the initial panel.
The clinical lesson is straightforward. If albumin is low, do not stop at the raw result. A corrected calculation may reveal that a seemingly normal gap actually reflects high anion gap metabolic acidosis. This is a critical part of accurate assessment and should be considered in any serious acid-base evaluation.
How to interpret results with the delta gap
The delta gap assists in determining whether the acidosis is a straightforward high-gap disorder or part of a mixed picture. It measures the rise in the anion gap to the drop in bicarbonate. The delta ratio then helps detect a possible mixed acid-base disorder.
In practice, the delta gap checks whether the change in the anion gap matches the expected bicarbonate deficit. If bicarbonate has fallen beyond expectation relative to the gap rise, there may be an additional normal-gap acidosis. If bicarbonate has not fallen as much as expected, there may be a concurrent metabolic alkalosis or chronic compensation.
The basic approach is:
- Estimate the increase in the anion gap above normal. Assess the decrease in bicarbonate below normal. Compare the two using the delta ratio.
This analysis is helpful because not all patients have a pure disorder. A person with high anion gap metabolic acidosis may also have vomiting, diarrhea, renal tubular processes, or other contributors. The delta gap offers a more complete view of https://anion-gap-values582.quantlynix.com/posts/what-causes-a-elevated-anion-gap-metabolic-acidosis the acid-base picture and improves diagnostic clue quality beyond the raw anion gap alone.
For a clinician, the big question is whether the result fits the expected pattern. If it does not, the patient may have a mixed acid-base disorder that requires broader evaluation. That makes the delta analysis especially useful in intensive or emergency settings where rapid but accurate interpretation matters.
When a decreased anion gap may be clinically important
A decreased anion gap is often missed, but it can occasionally signal an serious underlying problem. The first step is to think about lab error, because testing errors or specimen problems are a frequent explanation. Running again the test is often appropriate before launching into a larger workup.
If the low result is reproduced, consider changes in proteins and electrolytes. Paraproteinemia, including multiple myeloma, can lower the gap because abnormal positively charged proteins shift the charge balance. This is one reason a low gap may be an initial clue to a plasma cell disorder.
Hypercalcemia can also contribute to a low gap, although it is less common. In addition, severe hypoalbuminemia can substantially reduce the measured anion gap and hide the real acid-base pattern. That is why albumin should be checked whenever the result seems surprisingly low.
Although a low value is not the classic pattern in metabolic acidosis, it should anion gap clinical significance not be dismissed. It may be the earliest clue that the reported number is distorted by protein abnormalities, a measurement issue, or a broader metabolic problem. Good interpretation means checking the result and relating it to the patient’s overall clinical presentation.
Frequently asked questions about anion gap calculation
What exactly is the anion gap formula?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate. Written another way, it is sodium − (chloride + bicarbonate). This calculation formula applies routine lab values from the serum chemistry panel to assess whether unmeasured anions are present.
What can a high anion gap mean in metabolic acidosis?
A high result suggests high anion gap metabolic acidosis, which usually means acids or other unmeasured anions have piled up. Typical causes include lactic acidosis, ketoacidosis including diabetic ketoacidosis, renal failure, uremia, toxic alcohols, and salicylates. The value is a helpful clue, not a final diagnosis.
How do you correct the anion gap for albumin?
Albumin correction adjusts the measured result upward when hypoalbuminemia is present. Because albumin is a major unmeasured anion, low levels can hide a true acid load. The exact correction method may vary, but the goal is to calculate a more accurate albumin-corrected anion gap and improve anion gap interpretation.
Can metabolic acidosis occur with a normal anion gap with metabolic acidosis?
Yes. Normal anion gap metabolic acidosis can occur when bicarbonate is lost and chloride rises to replace it, keeping the gap within the reference range. This pattern is different from high-gap states like lactic acidosis or ketoacidosis. So a normal number does not rule out metabolic acidosis; it only suggests a different mechanism.
When is it appropriate to a low anion gap be evaluated further?
A low result should be evaluated further if it is persistent, unexpected, or accompanied by other abnormal findings. First consider testing error, then assess albumin, calcium, and protein abnormalities. Confirmed low values may warrant evaluation for paraproteinemia and multiple myeloma, especially if the clinical picture supports it.
When using an anion gap calculator works best when it adds to a wider medical context rather than being used alone. The strongest method brings together electrolytes, albumin, acid-base status, and the overall clinical evaluation. That is how a basic number becomes a practical tool for identifying and managing metabolic acidosis.