What the anion gap Evaluates
The anion gap is a calculated value used to assess electrolyte balance and aid assessment of acid-base status. It assists clinicians interpret a laboratory result by calculating the difference between observed cations and measured anions in the blood. Because routine chemistry panels do not measure every charged particle, the anion gap offers insight into unmeasured anions that may be present during a metabolic disturbance.
An anion gap calculator is a practical diagnostic tool for checking blood chemistry quickly. It is especially useful when a patient has an electrolyte imbalance, since small shifts in sodium, chloride, bicarbonate, and related values can signal an underlying acid-base disorder. In simple terms, the calculation helps identify whether the blood has an excess of acids, an excess loss of base, or a pattern that reflects electrolyte shift physiology.
The anion gap is not a diagnosis by itself. It is part of broader acid-base analysis and should be interpreted alongside the full electrolyte panel, the serum bicarbonate level, and other clinical findings. Used well, it turns a basic chemistry snapshot into a more meaningful picture of acid-base balance.
How Chloride Shift Affects the Anion Gap
The chloride shift explains the transfer of ions that works to preserve electroneutrality in body fluids. In clinical interpretation, shifts in chloride often occur in response to shifts in bicarbonate. When bicarbonate falls, chloride may rise to maintain balance, which can keep the anion gap near normal even when an acid-base disorder is present.
This relationship is important because the chloride shift can hide or illuminate a metabolic problem. For example, if bicarbonate is lost through the kidneys or gastrointestinal tract, the body may retain or elevate chloride. The result is a pattern of normal anion gap acidosis, also called hyperchloremic acidosis. In this setting, the anion gap may not rise, even though the patient has clear metabolic acidosis.
By contrast, if acids accumulate and bicarbonate falls without a matching chloride increase, the anion gap rises. That pattern is more indicative of high anion gap acidosis. Understanding the chloride shift helps distinguish whether the chemistry reflects a gain of acids, a reduction in buffer, or a compensatory change in the buffer system.
For that reason, an anion gap calculator is especially valuable when reviewing chloride level changes. It helps relate the raw numbers to the underlying physiology and improves recognition of a true anion deficit versus a simple compensatory shift.
Anion Gap Formula and Calculator Inputs
The typical anion gap calculation relies on sodium, potassium, chloride, and bicarbonate. Many providers prefer the simplified formula:
Anion gap = Sodium − (Chloride + Bicarbonate)Some formulas also include potassium as well:
Anion gap = (Sodium + Potassium) − (Chloride + Bicarbonate)Either approach estimate the relationship between measured cations and anions. The calculator input values typically come from standard serum electrolytes or a chemistry panel. Because each lab may report varying units or reference intervals, the exact reference range should always be interpreted in context.
In practical use, the calculator requires accurate values for:
- Sodium, the principal measured cation Potassium, in some cases included in the formula Chloride, a major measured anion Bicarbonate, often reported as CO2 on chemistry panels
These numbers represent the patient’s current blood chemistry and help estimate whether there are excess unmeasured anions contributing to the result. A helpful way to think about the calculation is that it calculates the gap left behind by anions not listed directly on the panel.
In the right context, the anion gap calculator provides a quick diagnostic calculation that assists with bedside decision-making. However, it should always be reviewed as part of the full clinical picture rather than treated as a standalone answer.
Typical Values and Adjusted Anion Gap
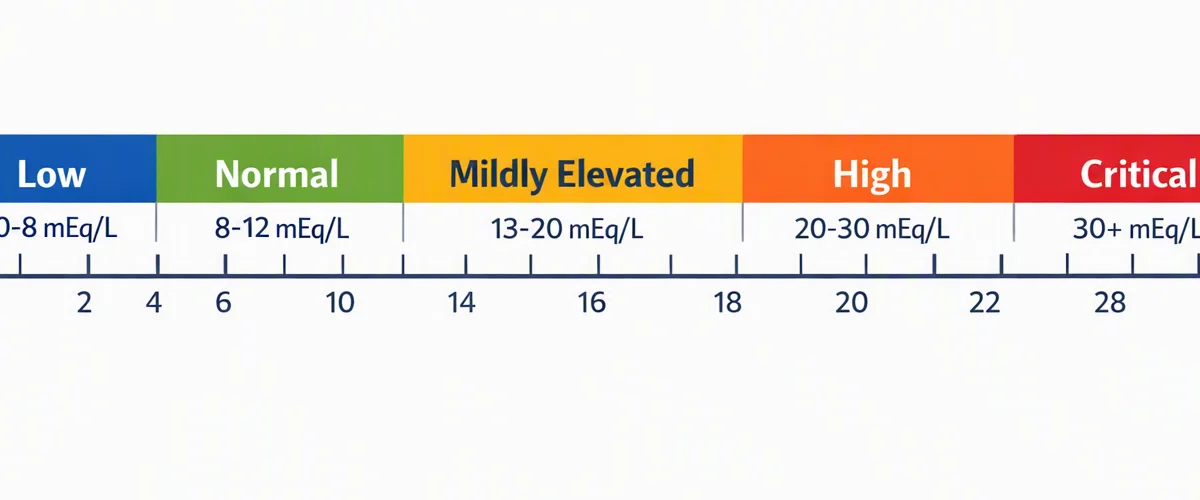
A typical normal anion gap changes a bit by laboratory procedure and whether potassium is added. Many clinicians regard as a value around 8 to 12 mEq/L normal when potassium is excluded, though the precise range should match the lab’s reference range. A normal result does not always eliminate illness; it may simply indicate that the electrolyte pattern is balanced in a way that does not increase the gap.
Albumin is a important unmeasured anion and has a strong effect on the anion gap. When albumin is low, the measured anion gap may appear falsely normal or low even if acids are present. This is why albumin correction matters so much in interpretation. In hypoalbuminemia, the corrected value can uncover hidden metabolic problems that the unadjusted number overlooks.
A corrected value calculates what the anion gap would be if albumin were normal. This is useful because low albumin reduces the anion contribution from the protein fraction, creating an apparent anion deficit. Without adjustment, a patient with serious acid retention may seem less abnormal than they truly are.
Albumin correction is particularly important in hospitalized patients, malnutrition, liver disease, or inflammation, where hypoalbuminemia is frequent. In these settings, the corrected value gives improved clinical interpretation than the raw number alone. It can also help avoid missing a mixed acid-base disorder.
High Anion Gap vs Typical Anion Gap Disorders
Acid-base acidosis is the general category most often reviewed with the anion gap. The central distinction is whether the gap is raised or is still normal. A high anion gap acidosis implies that acids or acid equivalents have built up, increasing the amount of unmeasured anions in the blood.
Common causes of high anion gap acidosis include lactic acidosis, ketoacidosis, and renal failure. In each case, the body is retaining or producing acids faster than they can be removed or buffered. The anion gap rises because bicarbonate is consumed while accompanying anions remain present in circulation.
A normal anion gap acidosis, on the other hand, usually reflects bicarbonate loss with a corresponding rise in chloride. This is where the chloride shift becomes medically important. The chloride increase helps preserve electroneutrality, but the tradeoff is a lower bicarbonate concentration and a persistent acidosis without a widened gap.
Identifying the difference matters because the causes and treatment strategies differ. High-gap disorders often prompt evaluation for toxic ingestion, tissue hypoxia, or severe metabolic crisis. Normal-gap disorders more often suggest gastrointestinal bicarbonate loss, renal tubular problems, or other patterns of chloride-related compensation.
Reading Results within Medical Context
The anion gap should be assessed alongside the full presentation, not on its own. An arterial blood gas assists identify whether the patient has acidemia, high pH, or a mixed acid-base picture. Meanwhile, serum electrolytes show whether changes in chloride, bicarbonate, or sodium account for the gap.
One useful concept is the delta gap, which contrasts the elevation in anion gap to the decrease in bicarbonate. That can help recognize mixed acid-base problems. For example, if the gap is elevated more than expected, there may be an additional metabolic alkalosis or chronic respiratory process. If the change is less than expected, there may be a concurrent normal-gap acidosis.
Clinical reading becomes more accurate when the anion gap is viewed as part of a broader acid-base analysis. A patient may have a high-gap metabolic picture on chemistry results, but the arterial blood gas may reveal compensation, overlap, or a second process. For this reason the anion gap calculator should support, not replace, clinical reasoning.
When reviewing a serum bicarbonate result, it is also important to note whether the bicarbonate drop fits the chloride rise. If chloride is elevated while bicarbonate is low, the pattern may support a normal anion gap acidosis. If chloride is not elevated and bicarbonate is low, an accumulation of acids is more likely.
Typical Causes of Irregular Findings
Abnormal anion gap results often point to a certain acid-base disturbance. A elevated gap may reflect lactic acidosis, ketoacidosis, renal failure, or exposure to toxins. These conditions increase acid load or decrease acid clearance, which raises anion concentration from unmeasured acids.
Lactic acidosis usually occurs when tissue oxygen delivery is impaired or when metabolism switches toward anaerobic pathways. Ketoacidosis may develop in diabetes, starvation, or alcohol-related states. Renal failure reduces the kidney’s ability to excrete acids and regenerate bicarbonate, leading to a progressively higher gap over time.
Normal-gap abnormalities are often caused by gastrointestinal loss of bicarbonate, such as diarrhea, or renal causes that waste bicarbonate. In these situations, chloride goes up to replace the lost base, which prevents the anion gap from widening. That makes the chloride shift a key clue in separating acid loss from acid accumulation.
Some toxins can also produce unusual patterns or mixed disorders. Because toxin-related states may change quickly, a single calculator result should never be used in isolation. Instead, it should be interpreted with the patient’s symptoms, medication exposures, renal function, and the full electrolyte panel.
Limitations of an Anion Gap Calculator
An anion gap calculator is useful, but it has restrictions. One important issue is laboratory variation. Different analyzers and reporting methods can alter the reference range, especially when potassium is counted or excluded. A result that appears abnormal in one setting may be appropriate in another.

Measurement error https://anion-gap-calculation.com/formula/delta-gap.html can also alter the outcome. Small inaccuracies in sodium, chloride, or bicarbonate may modify the gap enough to influence interpretation. This is particularly important when values are near the cutoff or when a patient has unusual physiology, such as severe dehydration, marked protein abnormalities, or mixed acid-base states.
Another limitation is that the calculator does not identify the source of the problem. It can suggest that the numbers point to an acid base issue, but it cannot tell whether the issue is lactate acidosis, ketoacidosis, renal failure, toxic exposure, or loss of bicarbonate. That requires history, examination, and additional testing.
Because of these factors, medical judgment remains essential. The tool works best as a support tool for clinical interpretation, not a substitute for complete evaluation. If the results do not match the patient’s condition, review the inputs again, verify the sample, and review the broader context.
FAQ About Anion Gap and Chloride Shift
What is an anion gap calculator used for?
An anion gap calculator is utilized to determine the discrepancy between recorded cations and anions in blood chemistry. It aids evaluate acid-base balance, recognize possible metabolic acidosis, and inform review of an acid-base disorder using results such as sodium, chloride, and bicarbonate.
How does chloride shift affect the anion gap?
The chloride movement may offset loss of bicarbonate by raising chloride, which may preserve the anion gap normal even when acidosis is present. This explains why a pattern of rising chloride with falling bicarbonate often indicates normal-gap acidosis, while a gap rise without chloride replacement indicates a raised-gap process.
What is the normal anion gap range?
The normal anion gap depends on the lab and whether potassium is included in the formula. A lot of labs use a range around 8 to 12 mEq/L, but the exact reference range should always match the local method and reporting format.
How do albumin levels change the anion gap?
Albumin is a major unmeasured anion, so low albumin lowers the measured gap. In hypoalbuminemia, the raw result may miss the true acid load, which is why albumin correction is critical for accurate interpretation.
When should a high anion gap be considered urgent?
A high gap may be urgent when it is associated with severe symptoms, rapid breathing, altered mental status, shock, or suspected lactic acidosis, ketoacidosis, renal failure, or toxins. In those settings, prompt evaluation with arterial blood gas, serum electrolytes, and full clinical assessment is important.