What an anion gap calculator measures
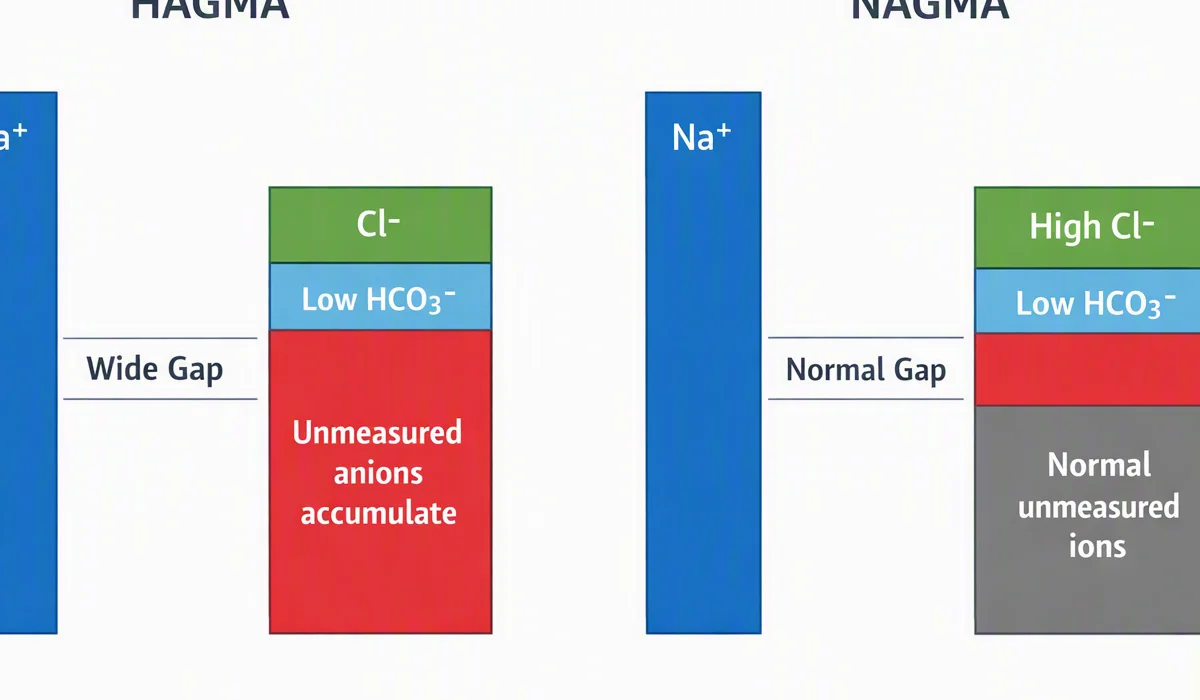
An anion gap calculator is used to estimate the difference between commonly measured cations and anions in the blood, usually using sodium, chloride, and bicarbonate. This calculation is a quick way to assess whether there are extra unmeasured anions contributing to an anion gap abnormality. In toxicology, that matters because certain poisons can create a dangerous acid-base disturbance before the cause is obvious.
The most common anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians also account for potassium, but the simplified version is used most often in routine electrolyte panel interpretation. The result gives a useful snapshot of serum bicarbonate loss or added acids in the bloodstream. For a patient with suspected poisoning, the calculator is not a diagnosis by itself, but it can quickly raise or lower clinical suspicion.
Because the gap depends on the measured serum electrolytes, it reflects the current state of the blood chemistry rather than a specific toxin. That is why it should be interpreted alongside symptoms, exposure history, blood gas results, and serum osmolality. In practice, the anion gap is one of the best screening tools for identifying a hidden metabolic derangement when the presentation is unclear.
Why toxic alcohol ingestion increases the anion gap
Toxic alcohol ingestion can lead to serious poisoning because the original alcohol and its metabolites disrupt normal metabolism. The classic agents are methanol and ethylene glycol, though propylene glycol can also contribute in some settings. These substances are toxic not only because of the compounds themselves, but because the body breaks down them into acidic metabolites that drive acid-base imbalance.
In methanol exposure, the metabolism produces formic acid, which contributes to high anion gap metabolic acidosis and can damage the optic system. That is why visual symptoms is such an important clue. In ethylene glycol exposure, metabolism creates glycolic acid and other acids that may lead to worsening acidosis and renal injury.
The anion gap rises because these acidic compounds act as hidden anions. As bicarbonate buffers the acid, the serum bicarbonate level falls, and the gap widens. This is why a patient may initially appear relatively stable but then rapidly develop an anion deficit and severe illness. The pattern is especially important when the history is incomplete and the presentation is only supported by subtle neurologic changes, abdominal symptoms, or unexplained acidosis.
Not every toxic alcohol behaves the same way. Isopropanol, for example, is classically associated with ketosis and central nervous system depression but does not usually cause the same high anion gap pattern because it is metabolized to acetone rather than a strongly acidic metabolite. That distinction is essential for reliable laboratory interpretation and next-step management.
How to determine the anion gap step by step
To operate an anion gap calculator accurately, first collect the most recent lab values from the chemistry results. Required values are the measured sodium, chloride, and bicarbonate. They are typically part of routine serum electrolytes and may be paired with additional toxicology studies, a blood gas, and a measured serum osmolality.
The basic steps are easy to follow:
- Find the sodium value. Identify the chloride value. Find the bicarbonate value. Sum chloride and bicarbonate together. Deduct that sum from sodium.
Example: if sodium is 140, chloride is 100, and bicarbonate is 12, then the anion gap is 28. This result is elevated and suggests a high anion gap metabolic acidosis. In the setting of possible poisoning, that number should trigger urgent review of the exposure history and lab context.
One useful refinement is the albumin correction. Because albumin is a major unmeasured anion, low albumin can make the measured anion gap look falsely normal or only mildly increased. The albumin-corrected anion gap helps account for that effect and improves diagnostic threshold accuracy. A common clinical approach is to adjust the gap upward when albumin is low so hidden acid accumulation is not missed.
This correction matters because patients with poisoning may also have poor nutrition, chronic illness, or fluid shifts that reduce albumin. Without adjustment, the calculator may underestimate the severity of the metabolic problem. In toxicology, careful use of the formula Extra resources improves clinical interpretation and prevents false reassurance.
Reading high anion gap results in suspected poisoning
A increased reading on an anion gap calculator does not prove toxic alcohol exposure, but it can strongly support it when matched by the relevant history and symptoms. The critical finding is high anion gap metabolic acidosis, which indicates excess acids or acid precursors in the bloodstream. In suspected poisoning, that finding should at once trigger a broader assessment of acid-base status.
One of the most useful companion tests is the osmolar gap, which measures measured serum osmolality with calculated osmolality. Early in toxic alcohol exposure, the osmolar gap may be elevated because the parent alcohol is still present. Later, as metabolism advances, the osmolar gap may fall while the anion gap rises. This shifting pattern is a classic clue in toxicology and can help assess the poisoning.
Clinical interpretation depends on timing. A patient who presents early may have a notable osmolar gap with only mild acidosis. A patient who presents later may show marked metabolic acidosis and a substantial anion gap, even if the osmolar gap is no longer striking. That is why the combination of clinical suspicion, laboratory interpretation, and exposure history is important more than any single value.
The presence of neurologic changes, visual complaints, rapid breathing, or evidence of kidney injury strengthens concern for toxic alcohol ingestion. A blood gas can show the degree of acidemia, while serum studies help reveal the metabolic derangement. If the pattern fits, urgent treatment should begin before confirmatory toxicology results return.
In suspected poisoning, a normal or borderline anion gap does not safely exclude toxic alcohol ingestion, especially if the patient presented early or has low albumin.
Frequent poisonous alcohols along with their lab patterns
Various toxic alcohols cause different patterns, and identifying them can speed up the timeliness of care. Methanol poisoning is typically associated with elevated anion gap metabolic acidosis and visual symptoms. Metabolic breakdown creates formic acid, which is directly toxic and contributes to both acidosis and eye injury. A patient may initially have general symptoms and later develop progressive neurologic symptoms or visual disturbance.
Ethylene glycol poisoning often appears with a similar-looking high anion gap pattern, but the metabolites are different. Ethylene glycol is converted to glycolic acid and other compounds that worsen acidosis and can damage the kidneys. Crystal formation may also contribute to kidney injury, so renal findings are particularly important. In practice, the blood gas, serum electrolytes, and osmolar gap together help build the case.
Isopropanol is a clear contrast because it usually causes an osmolar gap without the same degree of high anion gap metabolic acidosis. Instead, it may produce ketosis and central nervous system depression. That makes clinical interpretation distinct from methanol or ethylene glycol, even though all are toxic alcohols.
Propylene glycol is another important exposure, often associated to certain medications or solvent-containing products. It can contribute to metabolic acidosis and elevated osmolar gap depending on dose and metabolism. Although it is less common than methanol or ethylene glycol, it anion gap clinical significance belongs in the differential when laboratory patterns do not fit more common causes.
These patterns are not absolute. Timing, coexisting illness, and treatment can change the picture. Still, matching the lab pattern to the likely alcohol can make toxicology evaluation more targeted and can guide urgent treatment decisions.
Limitations of the anion gap calculator
The anion gap calculator is helpful, but it has important constraints. To begin with, albumin alters the reference level. Reduced albumin can reduce the measured gap and mask significant acid build-up, which is why the albumin-corrected anion gap is often more dependable in ill patients.
Second, many other conditions can also cause a high gap. Lactic acidosis can increase the gap in circulatory shock, hypoxia, seizures, or severe infection. Ketoacidosis from diabetes, starvation, or alcohol use can produce a similar pattern. Renal failure can result in retention of acids and unmeasured anions as kidney clearance declines. These are frequent alternative explanations that must be considered before labeling the problem as toxic alcohol ingestion.
Moreover, timing matters. A patient may present before enough metabolite has formed to elevate the gap. Another patient may present after the parent alcohol has already been metabolized, leaving a severe high anion gap but little or no osmolar gap. This makes serial assessment essential, especially when the exposure history is unclear.
Lastly, the gap is only one piece of the puzzle. A blood gas, serum osmolality, renal function tests, and toxicology consultation may all be needed for a accurate diagnosis. The calculator supports decision-making, but it does not replace comprehensive laboratory interpretation and bedside assessment.
When to seek emergency medical evaluation
Suspected toxic alcohol ingestion is a life-threatening emergency. If there is a clear exposure history, unexplained and persistent metabolic acidosis, or symptoms such as confusion, visual disturbance, severe vomiting, rapid breathing, or altered mental status, prompt evaluation is needed. Do not delay for symptoms to worsen.
Call poison control without delay for expert guidance. They can assist with interpreting the likely toxicology pattern and advise on next steps based on the substance, timing, and available labs. In parallel, the patient should be evaluated in the emergency department, where rapid lab testing and treatment can begin.
Specific treatments may consist of an antidote such as fomepizole or, in some settings, ethanol-based therapy, depending on clinical circumstances and local protocols. If the poisoning is severe, or if there is significant acidosis, end-organ injury, or high toxin burden, hemodialysis may be needed to remove the alcohol and its toxic metabolites.
Urgent treatment is especially important when there are neurologic symptoms, worsening kidney injury, or a steadily increasing anion gap. The earlier therapy begins, the better the chance of preventing permanent injury. In toxic alcohol cases, waiting for confirmatory testing can be risky.
Frequently asked questions on anion gap and toxic alcohols
What does a anion gap calculator show in suspected toxic alcohol ingestion?
An anion gap tool shows whether there is a gap between measured cations and anions, using sodium, chloride, and bicarbonate. In suspected toxic alcohol ingestion, a high result suggests extra unmeasured anions from toxic metabolites and raises concern for high anion gap metabolic acidosis. It is most useful when combined with the osmolar gap, blood gas, and exposure history.
How is the anion gap calculated from sodium, chloride, and bicarbonate?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate. If sodium is 138, chloride is 102, and bicarbonate is 14, the anion gap is 22. Many clinicians also apply an albumin correction when albumin is low so the result better reflects overall acid-base status.
What's the difference between anion gap and osmolar gap?
The anion gap reflects unmeasured anions in the blood, while the osmolar gap reflects unmeasured osmotically active substances in serum osmolality. In toxic alcohols, the osmolar gap may be high early because the parent alcohol is present, while the anion gap rises later as acidic metabolites accumulate. Both are important in lab interpretation.
Can a normal anion gap rule out methanol or ethylene glycol poisoning?
No. A normal anion gap does not rule out methanol or ethylene glycol poisoning, especially early after exposure or when albumin is low. The osmolar gap, blood gas, and clinical suspicion may still support toxic alcohol ingestion before the anion gap becomes elevated. Serial testing is often necessary.
When does someone with suspected toxic alcohol ingestion seek emergency care?
Emergency care is needed right away if there is suspected exposure plus symptoms such as confusion, visual disturbance, severe vomiting, rapid breathing, or collapse. Contact poison control and go to the emergency department without delay. Severe cases may require an antidote and hemodialysis to prevent worsening metabolic acidosis and organ damage.