What’s the Anion Gap?
The anion gap is a calculated value used to help evaluate acid-base balance and detect certain kinds of electrolyte imbalance. It comes from a typical serum chemistry panel and weighs measured positively charged ions with measured anionic ions in the blood. In clinical practice, it allows clinicians detect a hidden metabolic derangement that may not be obvious from symptoms alone.
The classic calculation uses serum sodium, serum chloride, and serum bicarbonate. These electrolytes are part of the body’s buffering system, which works to maintain stable pH. When the balance shifts, the anion gap can increase or stay unchanged depending on the underlying cause of the problem.
One reason the anion gap is useful is that it acts as a diagnostic clue during a medical evaluation. A changed gap can point toward a specific acid-base disorder, especially metabolic acidosis. It is not a diagnosis by itself, but it can help narrow the differential diagnosis and direct follow-up testing.
The normal reference range varies somewhat by laboratory because of differences in measurement methods and reporting. That is why the lab’s own result range matters more than a single universal number. Still, the basic concept remains the same: the anion gap reflects the difference between measured ions and can reveal an anion deficit or an excess of unmeasured acids.
How the Anion Gap Calculator Works
An anion gap calculator is a rapid medical tool that uses the standard formula to readings entered from a serum chemistry panel. Most calculators use sodium, chloride, and bicarbonate. A few also include potassium, depending on the formula being used and the institution’s preference.
The most common formula is:

Anion gap = sodium - (chloride + bicarbonate)
When potassium is included, the formula becomes:
Anion gap = sodium + potassium - (chloride + bicarbonate)
The calculator yields a calculated value that aids assess whether an acid load is present. In clinical use, this is more than a math exercise. It is a screening tool that can indicate whether a patient may have metabolic acidosis and whether the pattern suggests a elevated-gap or normal-gap process.
Because the result is influenced by measurement technique and lab-specific calibration, the calculator should always be interpreted in context with the rest of the laboratory result. It works best as part of a broader clinical interpretation rather than as a stand-alone number.
For example, low bicarbonate with a high gap suggests accumulation of unmeasured acids. Low bicarbonate with a normal gap often suggests a loss of bicarbonate rather than acid accumulation. That distinction is key to understanding the test.
Anion Gap Metabolic Acidosis: What the Result Indicates
Metabolic acidosis means the blood has grown more acidic because bicarbonate has fallen, acid has gone up, or both. The anion gap helps classify the problem into high anion gap metabolic acidosis or normal anion gap metabolic acidosis. This classification gives an important diagnostic clue about the likely mechanism.
A high anion gap usually indicates the presence of unmeasured acids. These acids consume bicarbonate during buffering, which raises the gap. This pattern often points to problems such as lactic acid buildup, ketone production, kidney dysfunction, or ingestion of certain toxins.
A normal anion gap result does not mean the patient is normal. It usually means bicarbonate has been lost and chloride has risen to maintain electrical neutrality, producing a pattern often called hyperchloremic acidosis. This is a different type of acid-base imbalance and requires a different approach.
Recognizing the pattern matters because the treatment depends on the cause. A patient with high-gap acidosis may need urgent assessment for sepsis, hypoperfusion, diabetes, or toxin exposure. A patient with normal-gap acidosis may need evaluation for gastrointestinal losses, renal tubular defects, or medication effects.
In short, the anion gap is a practical way to recognize the biochemical signature of acid-base balance disturbances. It helps clinicians move from a general finding of metabolic acidosis to a more specific investigation of the underlying cause.
How to Work Out the Anion Gap Step-by-Step
Finding the anion gap is simple when you have the main electrolyte values. The standard steps use sodium, chloride, and bicarbonate, with possible inclusion of potassium.
- Step 1: Collect the serum electrolyte values from the lab report. Step two: Verify the values for serum sodium, serum chloride, and serum bicarbonate. Then: Add chloride and bicarbonate together. Finally: Deduct that sum from sodium.
With the basic formula:
Anion gap = sodium - (chloride + bicarbonate)
If the calculator uses potassium, include it to the sodium value before subtracting the other electrolytes. Potassium is usually a smaller component of the formula, but it can a bit change the result.
For example, if sodium is 140, chloride is 102, and bicarbonate is 22, the calculation is 140 - (102 + 22) = 16. If potassium is included and is 4, the calculation becomes 140 + 4 - (102 + 22) = 20.
That number is then reviewed with the lab’s reference range. Some labs consider a upper range normal, while others use a smaller one. The key is to assess the result using the specific reference range attached to the patient’s lab system.
Even when the arithmetic is easy, the meaning is not. The calculated result should always be evaluated in the setting of the patient’s symptoms, other test results, and overall clinical interpretation.
Adjusted Anion Gap and Albumin Correction
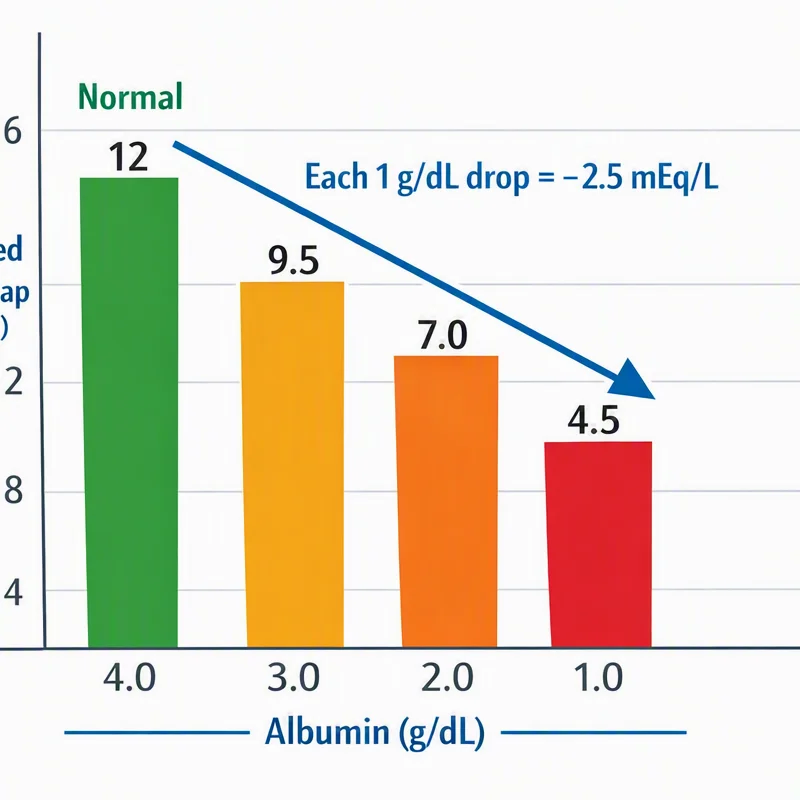
Albumin has a significant effect on the anion gap because it is one of the chief unmeasured anions in blood. When albumin is decreased, the measured anion gap may look artificially normal even when a clinically significant acidosis is present. This is why the corrected anion gap matters.
Hypoalbuminemia reduces the baseline gap by diminishing the amount of unmeasured negative charge in the plasma. In patients with low albumin, failing to adjust can obscure a high-gap process. The correction helps provide a more accurate estimate of the true acid burden.
A commonly used corrected formula includes a small amount to the measured anion gap for every decrease in albumin below the normal range. The exact adjustment may differ by institution, but the principle is the same: low albumin means the observed value may miss the actual disturbance.
This is why the corrected value is often more clinically meaningful than the raw number. A patient with an apparently normal laboratory result range may still have an elevated corrected gap if albumin is reduced. That can alter the interpretation from normal to concerning for hidden high-gap metabolic acidosis.
Albumin adjustment is especially important when the clinical picture indicates serious illness but the uncorrected anion gap does not match. In that setting, the corrected anion gap can identify an important metabolic problem and enhance the quality of the diagnostic workup.
Frequent Causes of High Anion Gap Metabolic Acidosis
High anion gap metabolic acidosis develops when acids collect in the body at a faster rate than they can be cleared. The excess acids use up bicarbonate and widen the gap. The leading https://anion-gap-results617.lucialpiazzale.com/how-to-operate-an-anion-gap-calculator-online causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohol ingestion.
Lactic acidosis develops when oxygen delivery or utilization is compromised, leading to lactate elevation. This can happen in shock, severe infection, hypoxia, seizures, or tissue ischemia. Lactate is an useful clue because it often signals a significant underlying cause that needs urgent treatment.
Ketoacidosis is usually related to uncontrolled diabetes, starvation, or alcohol use. In this situation, ketone accumulation adds to the acid load. The resulting metabolic derangement may present with nausea, vomiting, abdominal pain, dehydration, or altered mental status.
Renal failure can also cause a high gap because the kidneys cannot excrete acids effectively. As acid builds up, the anion gap rises and bicarbonate falls. This pattern may appear slowly in chronic kidney disease or more abruptly in acute kidney injury.
Toxic alcohol ingestion is another important cause, especially when the presentation is severe or unexplained. Certain ingestions generate acids that expand the gap and can cause dangerous neurologic, metabolic, and visual complications. When the history is uncertain, the anion gap may become an initial warning sign.
These conditions are part of the key differential diagnosis for a high-gap result. The calculator does not identify which one is present, but it helps guide the next tests and the urgency of care.
Common Reasons of Normal Anion Gap Metabolic Acidosis
Standard anion gap metabolic acidosis occurs when bicarbonate is removed and substituted by chloride, leaving the overall gap within the reference range. It is often called hyperchloremic acidosis because chloride rises as bicarbonate falls.
A common cause is diarrhea, which causes direct gastrointestinal bicarbonate loss. The body compensates by retaining chloride, and the result is a low bicarbonate state with a normal gap. This pattern is often noted in volume depletion as well.
Renal tubular acidosis is another significant cause. In this condition, the kidneys fail to acidify urine or conserve bicarbonate appropriately. The result is an acid-base disorder that can persist despite a seemingly ordinary anion gap.
Other causes of normal-gap acidosis may involve medication effects, urinary diversion, or certain kidney disorders, but the major teaching point is simple: the presence of acidosis does not always mean the gap is elevated.
In normal-gap states, the chemistry often shows a chloride shift as bicarbonate declines and chloride goes up. This compensation preserves electrical neutrality but indicates a real metabolic problem that still needs a cause-specific evaluation.
Clinical Assessment and Next Steps
Reviewing the anion gap is most useful when considered alongside the rest of the patient’s data. When the result suggests acidotic state, the next step is usually a specific diagnostic workup. This evaluation may include an ABG, blood lactate, ketones, kidney function testing, and sometimes toxin screening.
An ABG gas aids determine the pH and ventilatory compensation. Blood lactate is valuable when lactic acidosis is considered. Ketone levels aid assess for diabetic or starvation-related ketoacidosis. Renal studies help determine whether reduced acid excretion is playing a role to the disorder.
This gap also aids in determining urgency. A very high value can indicate a potentially hazardous metabolic disorder that needs prompt attention. A normal gap paired with low bicarbonate may indicate another cause, for example gastrointestinal loss or renal tubular dysfunction.
Clinical interpretation also needs to consider complaints such as shortness of breath, mental confusion, dehydration, vomiting, stomach pain, or evidence of an infection. The test result is only one element of the picture, but it can be an important diagnostic clue that guides the next step in treatment.
Because of this, the anion gap calculator is best viewed as a preliminary tool that supports, rather than replaces, medical reasoning. It helps structure the differential diagnosis and streamline the evaluation effectively.
Drawbacks of an Anion Gap Calculator
An anion gap calculator is helpful, but it has major limitations. The first is lab variation. Various analyzers, measurement methods, and reference intervals can generate somewhat different results. So the same patient may be placed in different result categories depending on where the test was processed.
The second limitation is the albumin-related effect. If uncorrected, a reduced albumin level can hide a genuine raised gap. This is one reason the anion gap correction is so vital in individuals with hypoalbuminemia or serious illness.
Another issue is that the gap does not directly measure every relevant ion. Alterations in unmeasured cations, including ionized calcium, may affect interpretation in certain situations. The calculator also does not determine whether the acidosis is acute or chronic, nor does it reveal the exact underlying cause.
Most importantly, the number must be interpreted in clinical context. Symptoms, history, medications, kidney function, and other lab results all influence the meaning of the calculation. A normal value does not exclude disease, and an elevated value does not prove one specific diagnosis.
Used well, the calculator is a helpful clue. Used alone, it can be misleading. That is why it should always support broader medical evaluation rather than replace it.
Frequently Asked Questions
What is an anion gap calculator used for?
An anion gap calculator is used to estimate the gap from serum electrolytes and help assess metabolic acidosis. It acts as a screening tool for an acid-base disorder and can point toward a high-gap or normal-gap pattern. Clinicians use it to guide clinical interpretation and direct the next diagnostic steps.
How do you calculate the anion gap in metabolic acidosis?
The usual formula is sodium - (chloride + bicarbonate). Some versions also include potassium. The calculation uses values from the serum chemistry panel and produces a calculated value that is compared with the lab’s reference range.
What does a high anion gap mean?
A high gap usually means there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohol ingestion. It suggests a high anion gap metabolic acidosis and usually warrants a focused diagnostic workup.
Why do you correct the anion gap for albumin?
You correct it because albumin strongly affects the measured gap. With hypoalbuminemia, the uncorrected result may look normal even when a true metabolic acid load is present. The corrected anion gap gives a more accurate picture of acid-base balance and helps avoid missed diagnoses.
Which conditions can cause a normal anion gap metabolic acidosis?
Common causes include intestinal fluid loss, renal tubular acidosis, and additional problems that result in loss of bicarbonate with a compensatory increase in chloride, often referred to as hyperchloremic acidosis. Even though the gap is normal, the patient still has a true metabolic acidosis that requires evaluation.