What’s the Anion Gap?
The anion gap is a clinical measurement used to assist assess acid-base disorders and recognize patterns in serum chemistry. It examines the main measured cations and anions in blood, mainly sodium and chloride, along with bicarbonate and sometimes potassium. This makes it a practical tool for spotting an electrolyte imbalance that may not be obvious from a quick look at the lab panel.
In routine practice, the anion gap serves as a form of laboratory interpretation and clinical decision support. When the gap is elevated, it often points to the presence of unmeasured anions from an underlying metabolic derangement. When the gap is low, it may suggest albumin loss, lab variation, or other less common issues. Because it is a window into the body’s acid-base state, the anion gap is a important part of a broader diagnostic framework.
The concept is especially important in metabolic acidosis evaluation, where it helps separate high anion gap metabolic acidosis from normal anion gap metabolic acidosis. That distinction helps guide the next steps in patient assessment and can focus the search for causes quickly.
Calculating the Anion Gap
The usual anion gap formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
Some clinicians include as well potassium in the equation, but the typical version leaves it out because potassium contributes relatively little to the final value. When included, the formula becomes:
Anion gap = (serum sodium + potassium) − (serum chloride + serum bicarbonate)
To apply the calculation correctly, you need values from a basic metabolic panel or an equivalent electrolyte panel. The key inputs are serum sodium, serum chloride, and serum bicarbonate. These values are part of routine serum chemistry testing and are commonly available in hospital and outpatient settings.
A quick example helps show the math:
- Sodium: 140 Chloride: 102 Bicarbonate: 24
The anion gap would be 140 − (102 + 24) = 14.
This medical calculation is not just about arithmetic. The result should be read in context, especially when evaluating metabolic acidosis or other acid-base abnormalities. Small differences in lab methods and normal variation can affect the final number, which is why the reference range matters.
How to Operate an Anion Gap Calculator
An Anion Gap Calculator can speed up the process of laboratory interpretation by turning raw laboratory values into an immediate result. This is useful in contexts where quick clinical decision support helps determine whether a patient needs further evaluation for an acid-base problem.
The basic calculation steps are easy:
- Provide the serum sodium value. Provide the serum chloride value. Provide the serum bicarbonate value. If needed, enter potassium if the calculator allows it. Compare the result against the expected reference range.
Many calculators also include albumin correction, which is essential when serum proteins are abnormal. Since albumin is a major unmeasured anion, low levels can make the measured gap look artificially normal or low. A calculator that adjusts for this can provide a more precise corrected value.
Use the result as a diagnostic aid, not as a standalone diagnosis. The anion gap is one part of a full acid-base analysis that may also include blood gas data, clinical context, and additional labs. In that sense, the calculator supports both rapid screening and deeper metabolic acidosis evaluation.
Typical Anion Gap vs Increased Anion Gap Metabolic Acidosis
A key use of the anion gap is differentiating normal anion gap metabolic acidosis from high anion gap metabolic acidosis. Both are forms of metabolic acidosis, but they point to different processes and distinct causes.
In normal anion gap metabolic acidosis, bicarbonate is reduced or chloride rises to take its place, so the gap stays inside the usual reference range. This pattern often reflects a hyperchloremic process rather than an accumulation of acids. It is still an important acid-base disorder and should not be dismissed simply because the gap is normal.
In high anion gap metabolic acidosis, excess acid or acid precursors introduce unmeasured anions to the blood. That raises the gap and signals a different class of pathology. This is a key clue in acid-base disorders because it often shifts the differential diagnosis substantially.
The practical value of this distinction is that it focuses the interpretation guide. A patient with anion gap elevation needs evaluation for causes that produce acid accumulation, while a patient with a normal gap may need assessment for bicarbonate loss, renal tubular issues, or other non-gap processes. This approach strengthens the overall diagnostic framework.
Common Causes of Elevated Anion Gap
A number of well-known conditions cause anion gap elevation. The most common include lactic acidosis, ketoacidosis, renal failure, and ingestion of toxic alcohols. Each leads to accumulation of acids or acid byproducts that increase the number of unmeasured anions.
Lactic acidosis occurs when lactate builds up due to tissue hypoperfusion, shock, severe infection, seizures, or other states of impaired oxygen delivery. It is a frequent cause of high-gap acidosis and frequently requires urgent attention.
Ketoacidosis may occur in diabetes, prolonged fasting, alcohol use, or starvation states. Ketone bodies act as acids and raise the gap, so this diagnosis is often considered in metabolic acidosis evaluation when glucose or nutritional history suggests it.
Renal failure can also lead to a rising gap because the kidneys cannot excrete acid effectively, allowing organic acids to accumulate. Over time, this becomes a clear marker of worsening metabolic derangement.
Toxic alcohols, such as methanol or ethylene glycol, are dangerous causes of high-gap acidosis. Their metabolism produces acids that significantly increase the anion gap and require rapid recognition. In these cases, the gap may be an early clue even before all confirmatory testing is available.
Other causes can exist, but these are the high-yield diagnoses that most often appear in an interpretation guide. The goal is not just to identify the gap but to connect it to the likely source of the acid load.
Albumin Correction and Why It Counts
Low albumin may mask an increased anion gap because albumin is a major unmeasured anions in the bloodstream. When serum albumin is decreased, the measured anion gap may look misleadingly normal even when acid is present. That is why albumin correction is such an key step in clinical interpretation.
A albumin-corrected gap adjusts the measured number to compensate for the effect of low albumin. This is particularly important in ill patients, where albumin often declines because of inflammation, malnutrition, liver disease, or fluid shifts. Without the correction, an underlying elevated-gap disorder may be missed.
A commonly used albumin-adjustment formula adds a fixed amount to the measured gap for each reduction in albumin below normal. Different institutions may use slightly different versions, but the principle is the same: lower albumin lowers the expected gap. Because of this, the reference range may need to be interpreted in a different way when albumin is abnormal.
Albumin correction improves the usefulness of the Anion Gap Calculator as a diagnostic aid. It helps identify hidden lowered anion gap or a missed elevation and makes the result more accurate for overall evaluation. In practice, this means the raw number is only the starting point; the corrected result often tells the real story.
How the Anion Gap Works Within Acid-Base Analysis
The anion gap is simply one element in acid-base analysis. A full workup often includes an arterial blood gas, which supplies pH and measured bicarbonate levels, together with information about ventilation. Together, these data show whether the primary problem is metabolic, respiratory, or mixed.
When the blood gas shows acidemia and the anion gap is elevated, the clinician can more confidently pursue causes of high anion gap metabolic acidosis. If the pH is low but the gap is normal, the interpretation moves toward normal anion gap metabolic acidosis or another non-gap process.
Respiratory compensation also matters. In metabolic acidosis, the lungs often lower carbon dioxide to counteract the acid load. If compensation is suitable, the patient may be partially stabilized. If it is inadequate or excessive, another disorder may be present. That is why the anion gap should be used with the arterial blood gas rather than in isolation.
This broader diagnostic framework is essential in complex cases. A patient may have a metabolic acid-base disorder, but the blood gas and anion gap together reveal the true pattern. In this setting, the gap becomes a helpful pointer to the next step in the interpretation guide, not the final answer.
Common Analysis Errors
A number of pitfalls can lead to incorrect interpretations when evaluating the anion gap. One of the most common is lab error. Specimen contamination, processing problems, or measurement errors can distort sodium, chloride, or bicarbonate values and create a misleading result. If the number does not fit the clinical picture, repeat testing may be necessary.
A further problem is looking only at the total gap and missing the role of unmeasured anions or serum protein changes. Because albumin is such a major contributor, failing to correct for hypoalbuminemia can obscure an important elevation. Likewise, assuming a normal result excludes serious disease can be a mistake.
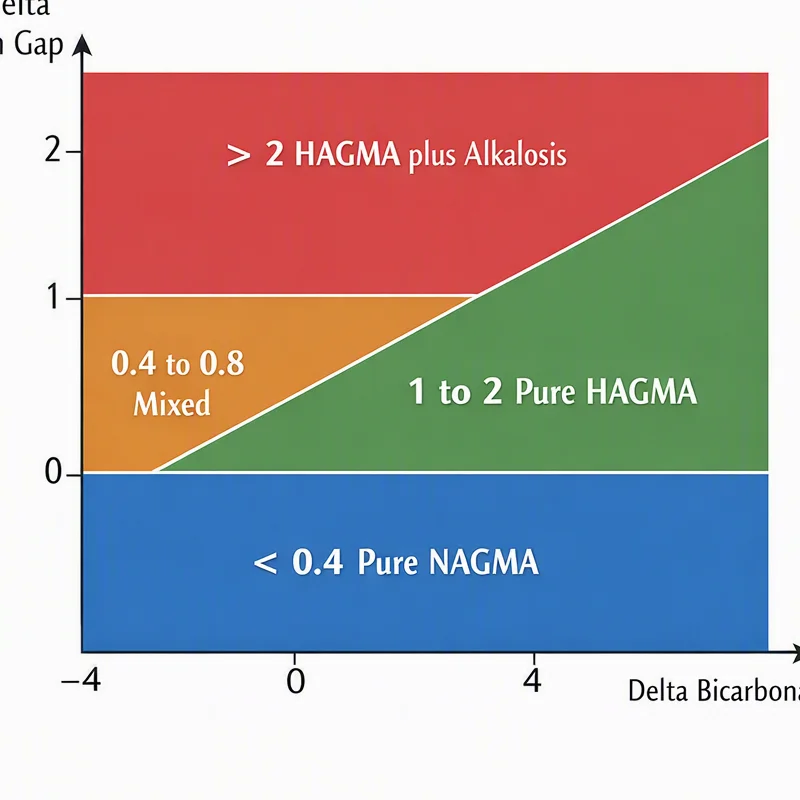
The delta gap is useful when evaluating mixed processes. It compares the change in the anion gap to the change in bicarbonate and can suggest whether another acid-base disorder is present. If the findings do not align, a mixed acid-base disorder may be hiding underneath the apparent primary problem.
This matters since a patient can have more than one process at the same time. For example, a high anion gap metabolic anion gap clinical significance acidosis may coexist with metabolic alkalosis or a concurrent respiratory issue. A careful look at the full serum chemistry, blood gas, and clinical context is the best way to avoid missing these overlapping abnormalities.
Common Questions
How large is a normal anion gap range?
The anion gap normal range depends on the lab method and whether potassium is included in the calculation. In many settings, the typical range is roughly in the single digits to low teens, but the exact reference range can vary by institution. Always interpret the result using the range reported by the laboratory and consider whether albumin correction is needed.
How is calculated the anion gap from lab values?
Use the anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. Some versions also include potassium. The values usually come from a basic metabolic panel. An Anion Gap Calculator can perform the clinical calculation quickly and https://anion-gap-reference252.scriblorax.com/posts/anion-gap-calculator-for-medical-center-lab-analysis reduce arithmetic errors during laboratory interpretation.
Why does low albumin affect the anion gap?
Low albumin reduces the amount of negatively charged serum proteins in blood, which can lower the measured gap. That means a patient with a real acid-base problem may appear to have a normal result unless albumin correction is applied. A albumin-corrected anion gap gives a more precise picture of the underlying disturbance.
Why is there a high anion gap?
Frequent elevated anion gap causes include lactic acid buildup, ketoacidosis, renal failure, and toxic alcohol ingestion. These conditions generate or retain acids that increase unmeasured acidic particles in the blood. When the gap is elevated, the result should be integrated with the arterial blood gas, patient history, and other laboratory findings.
In what situations should an anion gap be repeated or corrected?
Repeat or correct the anion gap when the result does not match the clinical picture, when laboratory error is possible, or when albumin is low. It should also be reviewed if the patient’s condition changes, if new metabolic acidosis is suspected, or if a mixed disturbance is being evaluated. In many cases, repeating the chemistry panel and applying albumin adjustment improves diagnostic accuracy.