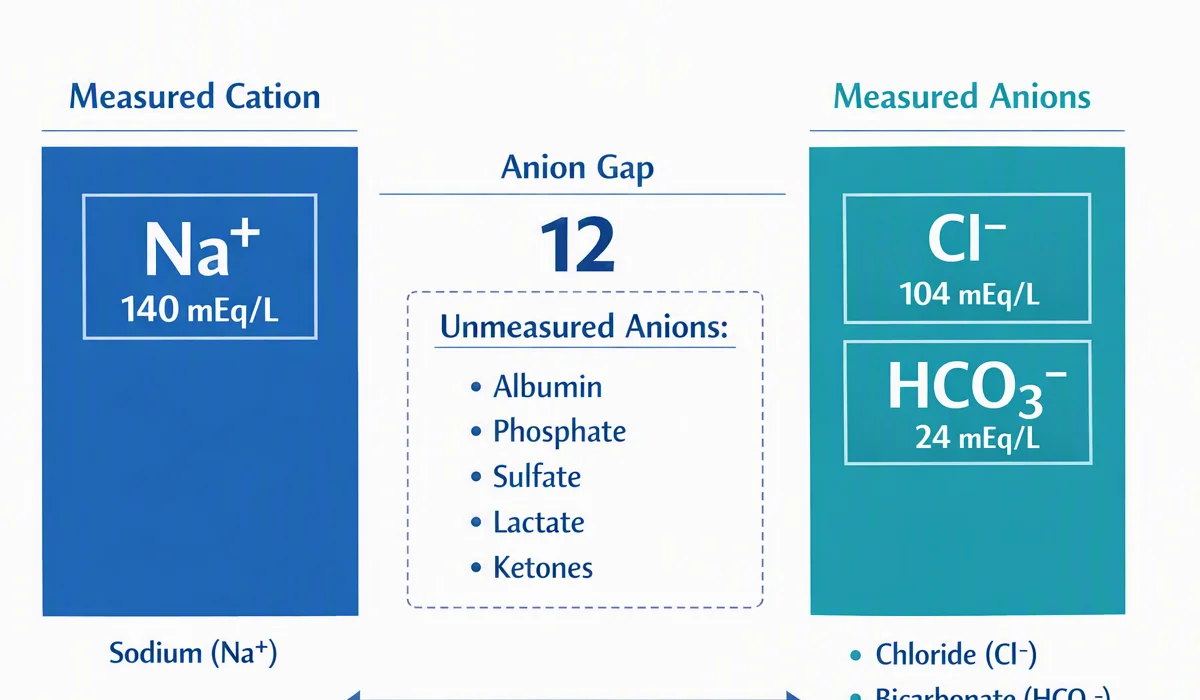
What the Anion Gap Indicates
The anion-gap value is a computed measure that helps doctors assess acid-base balance and identify hidden electrolyte abnormality. It is based on routine lab results from a blood test and reflects the disparity between measured positively charged ions and negatively charged ions in the blood.
In practice, the calculation uses sodium levels, chloride, and bicarbonate, with potassium sometimes included depending on the formula. The result gives insight into unmeasured acids that may be accumulating during illness. Because of that, the anion gap is a useful diagnostic tool for evaluating an acidotic condition and narrowing the causes of acid buildup.
Most clinicians first review a standard metabolic panel or a blood gas when acid-base problems are suspected. The anion gap can then help determine whether the patient has elevated anion gap metabolic acidosis or non–anion gap metabolic acidosis. That distinction matters because the underlying causes, severity, and next steps can be very different.
Although the calculation is simple, the interpretation is not. The value is only one piece of the broader clinical interpretation of the patient’s condition. It should be considered alongside symptoms, medications, kidney function, glucose, lactate, ketones, and other test results.
How to Operate an Anion Gap Calculator
An anion gap calculator automates the gap calculation so you can easily interpret the result from a blood chemistry panel. To use it, enter the serum sodium, chloride, and bicarbonate values. Some calculators also support input for albumin and potassium, which improves accuracy in certain cases.
The main advantage of a calculator is speed and consistency. It reduces arithmetic mistakes and helps organize the evaluation of metabolic derangement. In many cases, the calculator will also display a corrected result if the serum albumin is low, anion gap clinical significance since hypoalbuminemia can reduce the apparent gap and mask clinically important disease.
A practical workflow can be followed this way:
- Examine the basic metabolic panel or blood gas. Enter serum sodium, serum chloride, and bicarbonate. Add albumin if the calculator supports albumin correction. Check the calculated anion gap against the expected reference interval. If the gap is elevated, evaluate causes of metabolic acidosis. If the result is abnormal, consider whether a mixed acid-base disorder is present.
The calculator is most helpful when paired with the rest of the acid-base picture. A normal number does not automatically mean normal physiology, and an elevated number does not identify the cause by itself. It is a guide for further clinical interpretation, not a final diagnosis.
Formula for Anion Gap & Normal Ranges
The traditional anion gap formula reads:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians include potassium in the formula, but many modern calculators leave out it because the effect is small. When potassium is included, the result is slightly higher, but the same overall interpretive principles apply.
The normal anion gap is based on the lab method and the reference range reported by the laboratory. Different analyzers and measurement techniques can change the expected interval. That is why it is best to interpret the result using the lab’s own reference interval rather than a universal cutoff alone.
Albumin correction is essential because serum albumin is a major unmeasured anion. When albumin is low, the anion gap may appear falsely normal. Correcting for albumin helps reveal a hidden increase in unmeasured anions. This can be especially important in critically ill patients with metabolic acidosis.
A common clinical approach is to adjust the gap upward when albumin is below normal. The exact correction factor can differ by method, but the principle is the same: low albumin lowers the measured anion difference, so correction improves accuracy. For that reason, a good anion gap calculator often offers albumin correction as a built-in feature.
Understanding the formula also helps clarify the physiology. The serum contains measured cations and anions, but not all ions are directly measured. The gap represents the difference created by these unmeasured anions, making it a helpful window into hidden metabolic processes.
What exactly delta gap Means and Why It’s Important
The delta gap extends the reading of the anion gap by weighing the rise in gap to the drop in bicarbonate. This check helps identify whether the patient has only one acid-base problem or a mixed acid-base disorder. It is especially useful in metabolic acidosis when the clinician wants to know if another process is also affecting the bicarbonate level.
This is where the delta-delta ratio is used. The ratio compares the change in anion gap to the change in bicarbonate. If the ratio shows a mismatch, it may indicate an additional disorder such as metabolic alkalosis or another type of metabolic derangement occurring at the same time.
Why does this matter? Because not all cases of acidosis are clear-cut. A patient with high anion gap metabolic acidosis may also have vomiting, diuretic use, or other factors that shift bicarbonate in the opposite direction. The delta gap and normal AG values neonates delta-delta ratio help expose those overlapping patterns.
In short, the delta gap is a delta calculation that enhances the initial gap calculation. Instead of asking only whether the anion gap is elevated, it asks whether the increase in gap aligns with the expected drop in bicarbonate. That makes it an valuable tool for acid-base interpretation.
Sequential Delta Gap Analysis
To determine the delta gap, first find the measured anion gap from the chemistry values. Afterward compare it to the expected anion gap, which is often the upper end of the lab’s normal reference interval. The difference between the measured and expected values is the delta.
After that, compare that delta with the drop in bicarbonate. This comparison can help assess whether the bicarbonate loss is proportional to the increase in unmeasured acids.
A straightforward approach looks like this:
- Determine the measured anion gap. Locate the expected anion gap from the lab reference range. Deduct expected from measured to find the delta gap. Match that value with the change in bicarbonate. Interpret the pattern using the delta-delta ratio.
If the rise in anion gap is larger than the fall in bicarbonate, a second process such as metabolic alkalosis or preexisting elevated bicarbonate may be present. If bicarbonate falls more than expected, another acidifying process may be contributing. Either way, the result supports more nuanced acid-base interpretation.
This structured approach is particularly useful when the clinical picture is unclear. For example, a patient may have metabolic acidosis from one source and vomiting-related alkalosis from another. A basic gap calculation alone may miss that combination, but the delta gap can point toward a mixed acid-base disorder.
How to Understand Typical Findings
A high anion gap metabolic acidosis typically suggests there is accumulation of acidic compounds or other unmeasured anions. The most common clinical question is not simply if the gap is increased, but what is causing the increase and whether compensation is appropriate.
By contrast, normal-gap metabolic acidosis suggests that bicarbonate has been depleted and offset by chloride, so the gap falls within the reference interval. This pattern is frequently described as hyperchloremic acidosis because chloride goes up as bicarbonate decreases.
Breathing compensation should also be evaluated. In metabolic acidosis, the body generally boosts ventilation to decrease CO2 and partially restore pH. A blood gas can help determine whether the compensatory response is expected or whether another respiratory disorder is present.
Typical interpretation patterns include:
- Elevated anion gap metabolic acidosis with appropriate respiratory compensation. Normal-gap metabolic acidosis with elevated chloride and bicarbonate loss. Metabolic acidosis with a superimposed mixed acid-base disorder. Elevated gap with unexpected bicarbonate changes suggesting a second process.
Practically speaking, clinicians use the anion gap, delta gap, and blood gas together. The pattern is more important than any single number. A patient can look medically stable while having a substantial underlying metabolic problem, or appear quite ill with only small shifts in the measured gap.
Origins of Elevated Anion Gap
A expanded anion gap reflects build-up of unmeasured anions. Various major conditions can lead to this pattern, and the differential diagnosis depends on the overall clinical picture, medications, and other lab findings.
Lactic acidosis is a frequent cause and may occur with tissue hypoperfusion, sepsis, seizures, or severe illness. Elevated lactate introduces unmeasured acid to the blood and often results in high anion gap metabolic acidosis.
Diabetic ketoacidosis is a further classic cause. Ketone bodies accumulate and lower bicarbonate while increasing the gap. This is a key example of metabolic derangement where the anion gap calculator can promptly highlight the severity of the acid-base problem.
Renal failure can also elevate the anion gap because the kidneys cannot excrete acid properly. Retained acids and reduced clearance of metabolic byproducts can worsen the acidotic state.
Toxic alcohols are an significant and potentially dangerous cause. Methanol, ethylene glycol, and similar substances can generate acidic metabolites that increase the gap. In these cases, the gap may be only one clue among many, and urgent clinical assessment is essential.
Other causes may include medications, toxins, and inborn metabolic problems, but the major categories above are the most commonly emphasized. The key point is that an elevated anion gap signals a need to look for hidden acids, not simply to treat the number itself.
Sources of Normal Anion Gap Metabolic Acidosis
Normal anion gap metabolic acidosis usually reflects direct loss of bicarbonate rather than accumulation of hidden acids. As the lost bicarbonate is substituted with chloride, the serum chloride tends to rise, producing hyperchloremia.
Diarrhea is a classic cause because the gastrointestinal tract can lose large amounts of bicarbonate-rich fluid. This leads to metabolic acidosis with a normal gap and elevated chloride.
Renal tubular acidosis is another significant cause. In this condition, the kidneys cannot process acid and bicarbonate properly, resulting in persistent acid-base imbalance. Different forms of renal tubular acidosis can have different mechanisms, but they share the pattern of normal gap acidosis.
Bicarbonate loss can also occur through fistulas, certain medications, or renal causes. The common theme is that bicarbonate drops without a corresponding rise in unmeasured anions, so the anion gap may persist within range.
These patterns matter because they affect the workup. If the anion gap is normal, the next question is often whether the problem is gastrointestinal loss, renal tubular disease, or another cause of bicarbonate loss. The chloride level and blood gas results are especially helpful in that analysis.
Constraints and Clinical Caveats
Even a properly designed anion gap calculator has limitations. The biggest one is albumin correction. Because albumin is a major unmeasured anion, low serum levels can mask a true elevation in the gap. Without adjustment, a significant disorder may be missed.
Lab error is another caveat. Sample contamination, analyzer variation, or transcription mistakes can distort the result. If the value does not fit the clinical picture, repeat testing and review of the original basic metabolic panel may be necessary.
This calculated value also indicates the overall acid-base balance at a single moment. It does not indicate how quickly the disorder developed or whether the patient is improving. Changes over time can be more informative than a single measurement.
Finally, clinical context is essential. A mildly abnormal anion gap in a stable patient has a different meaning than the same result in someone with shock, altered mental status, or kidney injury. The calculator helps guide judgment, but it does not replace it.
For best results, evaluate the anion gap, delta gap, and blood gas together, then compare them with symptoms, medications, and the rest of the chemistry profile. That combined approach improves the chance of identifying mixed acid-base disorder and identifying the right underlying cause.
Frequently Asked Questions About Anion Gap and Delta Gap Calculators
What is an anion gap calculator used for?
An anion gap calculator is used to rapidly assess metabolic acidosis and identify whether the problem is likely to be a high anion gap metabolic acidosis or a normal anion gap metabolic acidosis. It helps clinicians read electrolyte patterns from lab values and decide whether further evaluation is needed.
How do you calculate the delta gap determined?
To calculate the delta gap, first find the measured anion gap, then compare it with the expected anion gap from the lab’s reference interval. The difference is compared with the drop in bicarbonate. This helps determine whether there may be a mixed acid-base disorder.
Why can albumin affect the anion gap?
Albumin is a major unmeasured anion, so lower albumin reduces the apparent anion gap. That is why albumin correction matters. Without it, a true gap elevation may be missed, especially in patients with significant illness or low serum albumin.
What is the meaning of a high anion gap mean?
A high anion gap often means there are extra unmeasured acid substances in the blood, such as those seen in lactic acidosis, diabetic ketoacidosis, renal failure, or toxic alcohols. It often indicates metabolic acidosis and should be read with the blood gas and overall clinical picture.
Can a normal anion gap also suggest metabolic acidosis?
Absolutely. Normal anion gap metabolic acidosis is frequent and often results from diarrhea, renal tubular acidosis, or other sources of bicarbonate loss. In this setting, chloride often increases to maintain electroneutrality, so the gap may remain normal even though the patient is acidotic.